




Extramammary Paget disease (EMPD) is an uncommon intraepithelial adenocarcinoma that can be primary or secondary. It is critically important to rule out secondary sources, particularly from the colon or gynecologic tract. Although EMPD most frequently affects the vulvar region, it can also occur in other areas, such as the anal region or even the axilla. Diagnosis is challenging, and treatment is often even more complex because of the lack of standardization, resulting in partial responses and frequent recurrences. Therapeutic options are diverse, reflecting the multifaceted nature of the management of this condition. Because of its multifocal nature, recurrence or persistence after treatment is common.1
A 72-year-old woman was referred to an oncologic dermatology center for a second therapeutic opinion. The patient had no relevant medical history and had experienced perianal itching and burning for 4 years. After unsuccessful treatment with topical corticosteroids, a biopsy confirmed the diagnosis of EMPD and ruled out a secondary origin. Topical imiquimod therapy was initiated but yielded no response. Over the subsequent 3 years before the current consultation, she underwent 3 conventional surgeries, 2 cycles of 5-fluorouracil, and 2 cycles of photodynamic therapy, with only partial responses.
Rectal and gynecologic origins of the disease were ruled out by physical examination, together with normal endoanal and gynecologic ultrasound findings. Preoperative mapping involved multiple biopsies around the visible lesions, which helped precisely delineate the resection area.
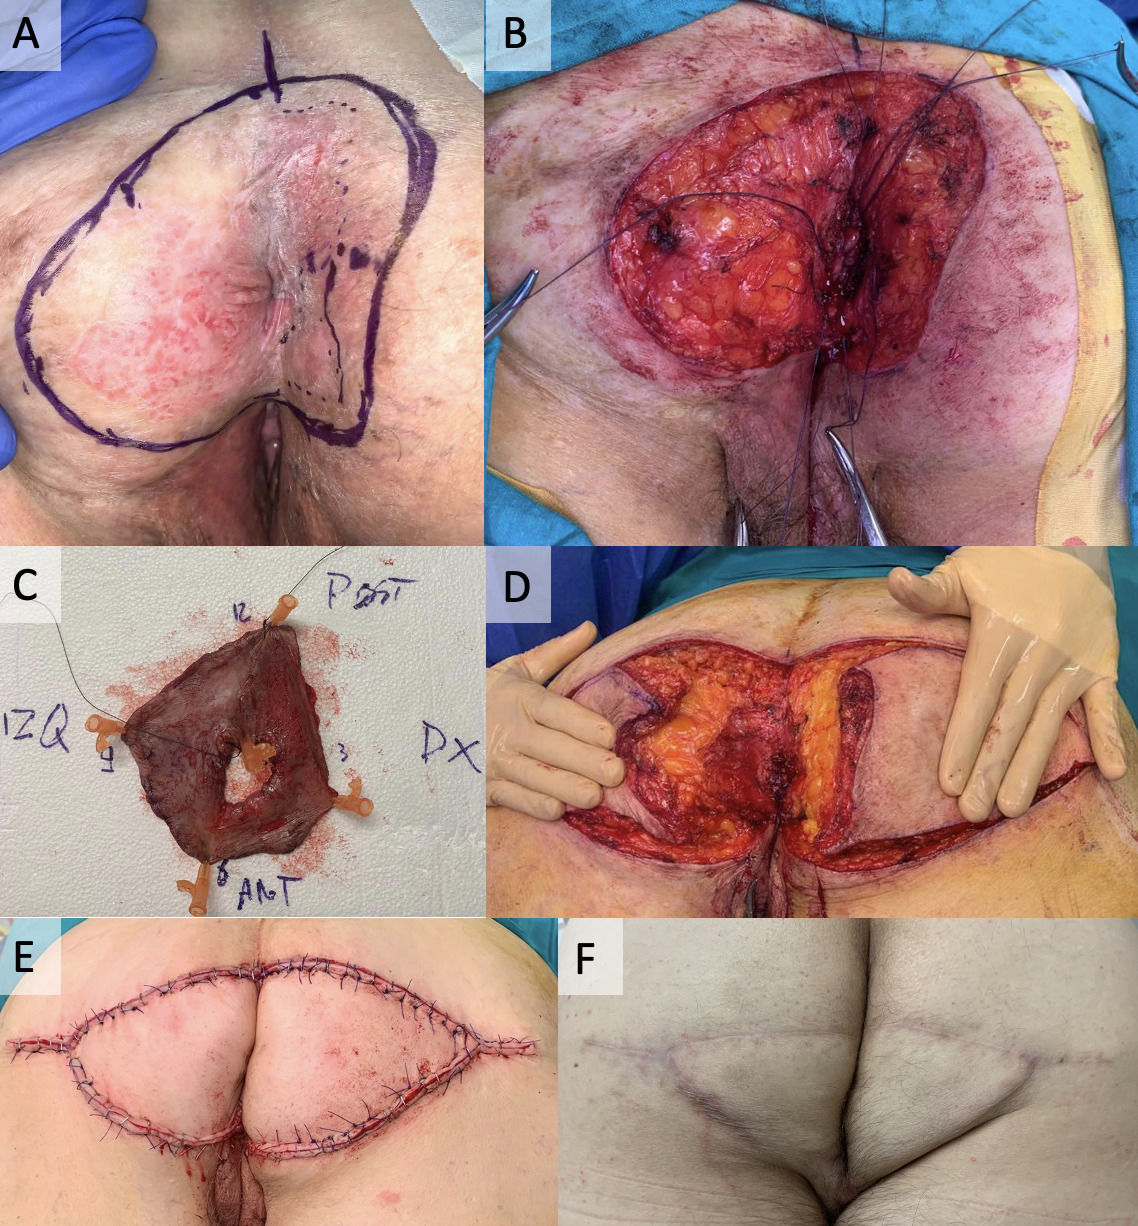
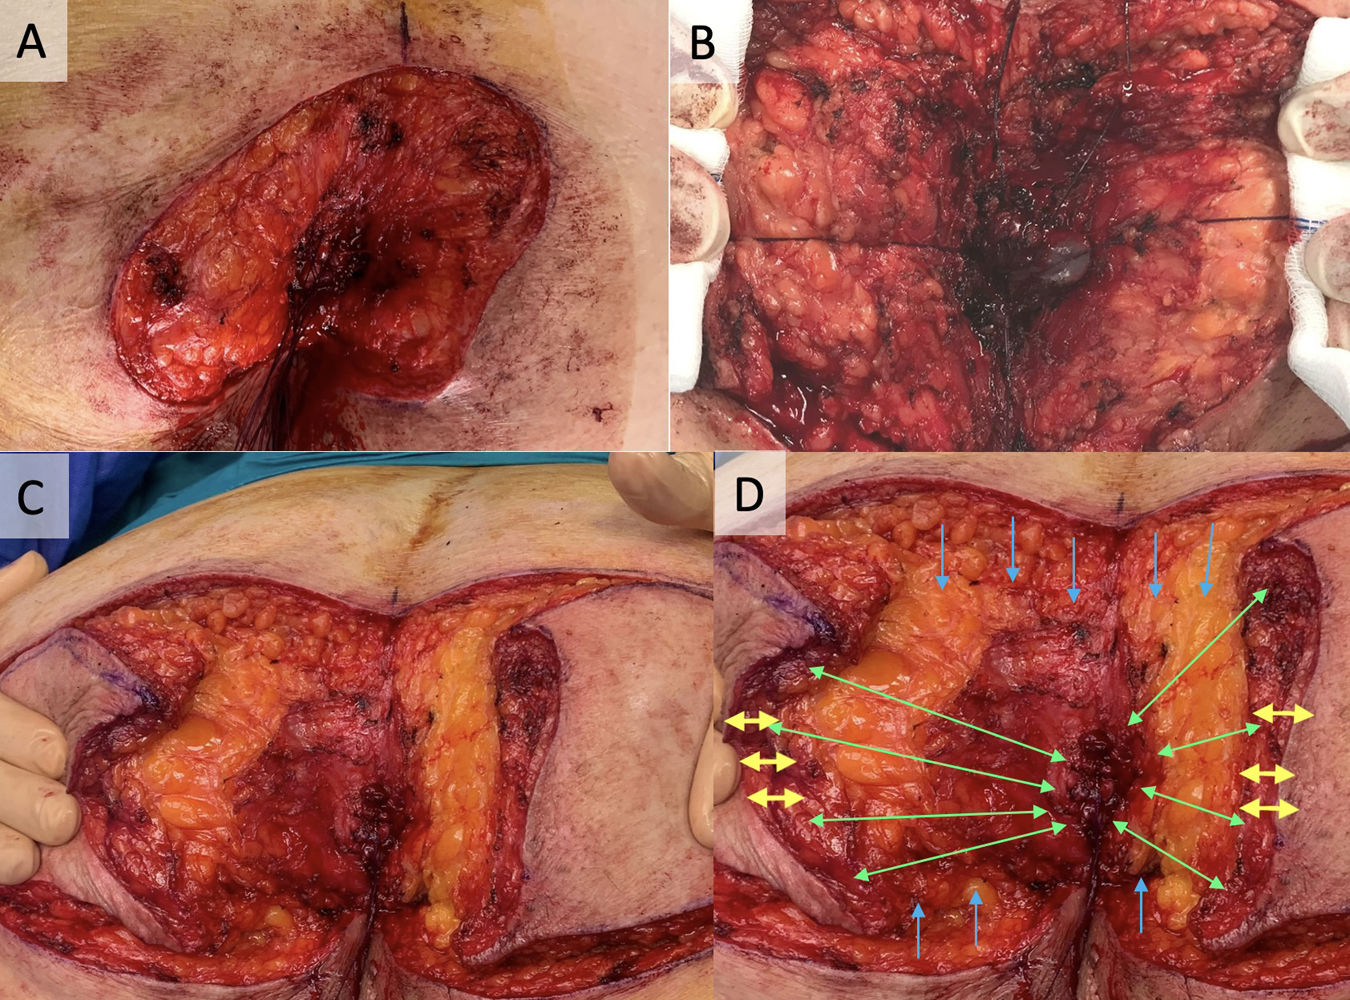
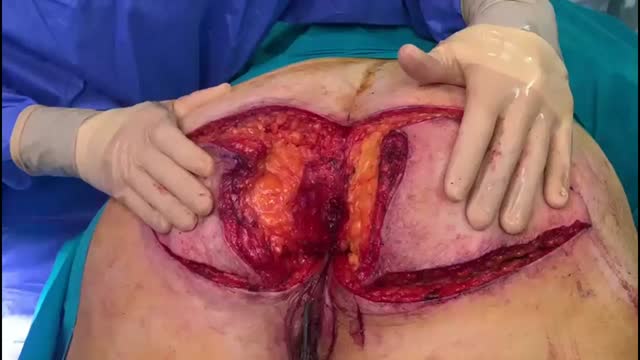
After confirmation of the diagnosis and surgical mapping (Fig. 1A), the marked skin and anal mucosa up to the dentate line were completely excised while preserving both the external and internal sphincters, with no need for fecal diversion. Deferred Mohs surgery using paraffin-embedded sections was performed. The postresection defect measured approximately 13cm×10cm (Fig. 1B) and was meticulously marked for histologic analysis using the Mohs technique (Fig. 1C). Bilateral fasciocutaneous V-Y island flaps were designed, harvested, and advanced toward the midline. The donor sites were primarily closed. The edge of each flap was sutured to the remaining anal mucosa (Fig. 1D and E; Video 1). Fig. 2 shows in detail how the endoanal reconstruction was performed: the operation was performed up to, but not including, the dentate line. The endoanal margins were marked, and the endoanal boundaries were then sutured to the deep edges of both island flaps (green arrows in Fig. 2D), with displacement of the upper and lower skin toward the anus also aiding flap closure (blue arrows in Fig. 2D). The new endoanal canal was maintained by suturing the skin in the inverted canal area (yellow arrows in Fig. 2D). To reconstruct the anal canal, the cut region of the endoanal area was sutured and everted toward the surface (detail in Fig. 2B). The dissection plane was located at least in the deep fat, above the gluteal fascia, and was based on the gluteal perforators, as in other island flaps.

Skin lesion and surgical procedure. Erythematous plaque with cotton-like whitish areas measuring approximately 10cm×8cm (Panel A). Defect after tumor excision (Panel B). Marking of the Mohs surgery specimen (Panel C). Design and advancement of bilateral V-Y island flaps (Panel D). Closure of the defect in the operating room (Panel E). Patient follow-up 3 months after surgery, with satisfactory functional and aesthetic outcomes (Panel F).

Detail of the endoanal reconstruction. Detail of the endoanal reconstruction, corresponding to the junction between the anal mucosa and the bilateral flap. The endoanal defect was sutured to the fatty region, corresponding to the deep region of the flap (green arrows in Panel D). Subsequently, the epidermis of both flaps was sutured, except in the central region, allowing creation of a new anal canal. Finally, the cranial and caudal margins of the defect were approximated to the endoanal region and sutured to the upper and lower skin regions (blue arrows in Panel D). Panel B shows the everted endoanal mucosa. In the anal canal area, to maintain the orifice, the skin mucosa, which would become the new mucosa, was inverted (yellow arrows in Panel D). Externalization of the endoanal mucosa produced sensory discomfort typical of mucosal externalization.
To prevent postoperative infection, given the location of the lesion and the duration of surgery (2.5h), amoxicillin–clavulanate, 1g IV, was administered 30min before surgery. After surgery, amoxicillin–clavulanate, 500/125mg, 1 tablet every 8h, was prescribed for 7 days. Postoperative care additionally included daily washing with lukewarm water and neutral soap. Sutures were removed after 15–20 days. The patient was instructed to avoid constipation to prevent restenosis. Histologic analysis confirmed EMPD, revealing intraepithelial adenocarcinoma cells with prominent Paget cells. Immunohistochemistry showed positivity for CK20, CDX2, and uroplakin, and negativity for PSA, CXCR4, and CXCR7. The margins were clear. At the 3-month follow-up (Fig. 1F), both functional and aesthetic outcomes were satisfactory, with no long-term anal incontinence reported. However, the patient reported a certain degree of “sensory incontinence,” in the form of dysesthesia and occasional itching, especially during defecation. No evidence of recurrence was observed either clinically or on endoanal ultrasound at the 18-month follow-up.
Extensive perianal resections, such as those performed for EMPD, may create large perianal defects that require reconstructive techniques. Because the perineal region is a highly functional anatomical area, it is essential to preserve anal continence and provide adequate soft tissue to avoid potential anal stenosis, which may lead to reinterventions or colostomies.
These radical excisions usually result in major defects with significant tissue loss, which are likely to be under considerable tension if primary closure is performed. This could jeopardize anal wound healing, leading to dehiscence and consequent morbidity. Secondary intention healing is a reliable option for managing minor defects. Closure by secondary intention is often performed in other entities, such as hidradenitis suppurativa, especially in large lesions or complex anatomical areas, including the perianal area, as in the present case.2
Most studies on split-thickness skin grafts to cover perineal defects have reported adequate cosmetic outcomes and good short-term results with minimal morbidity. Compared with other procedures, grafting is technically simpler. Nevertheless, it may be associated with unfavorable long-term results due to subsequent contamination or anal stenosis caused by secondary graft contraction and ectropion, with associated itching.3
Local skin flaps, as well as gluteus maximus and thigh myocutaneous flaps, have been widely used with remarkable results to reconstruct perineal tissue loss.4 However, it should be borne in mind that transposition or rotation flaps may displace the primary resection borders to other areas, resulting in poor monitoring of tumor recurrence.
Bilateral V-Y island flaps have been used for decades and constitute a reliable option to cover large perineal defects. In our institution, they are often performed as a trustworthy and simple procedure to manage major defects after EMPD resection.5 The postoperative period is painless and easy to manage, requiring only measures to prevent constipation and avoidance of pressure on the flap during approximately the first 10 days, and donor-site morbidity is minimal. However, large bilateral island flap procedures for gluteal defects may pose challenges, including an increased risk of compromised blood supply, prolonged wound healing, and potential postoperative complications such as flap necrosis or infection. Close monitoring and meticulous surgical technique are crucial to mitigate these risks and ensure successful outcomes.5,6
Considering that EMPD is a superficial and multicentric disease and that anal surgery can compromise sphincter function, topical or ablative treatments may be plausible alternatives to surgery for perianal lesions.3
With this case report, we emphasize the use of bilateral fasciocutaneous V-Y island flaps as a reliable alternative for “like-with-like” reconstruction of considerable perianal defects after EMPD resection. Furthermore, the described technique is versatile because it can be performed not only in cases of extramammary Paget disease but also in other scenarios, such as pressure ulcers or long-standing wounds.
EthicsPatient consent was obtained for publication of the image.
FundingNone declared.
Conflicts of interestNone declared.
Data availabilityThis work has not been published or presented elsewhere, in part or in its entirety. All data involved in this study are included in this published article.




