




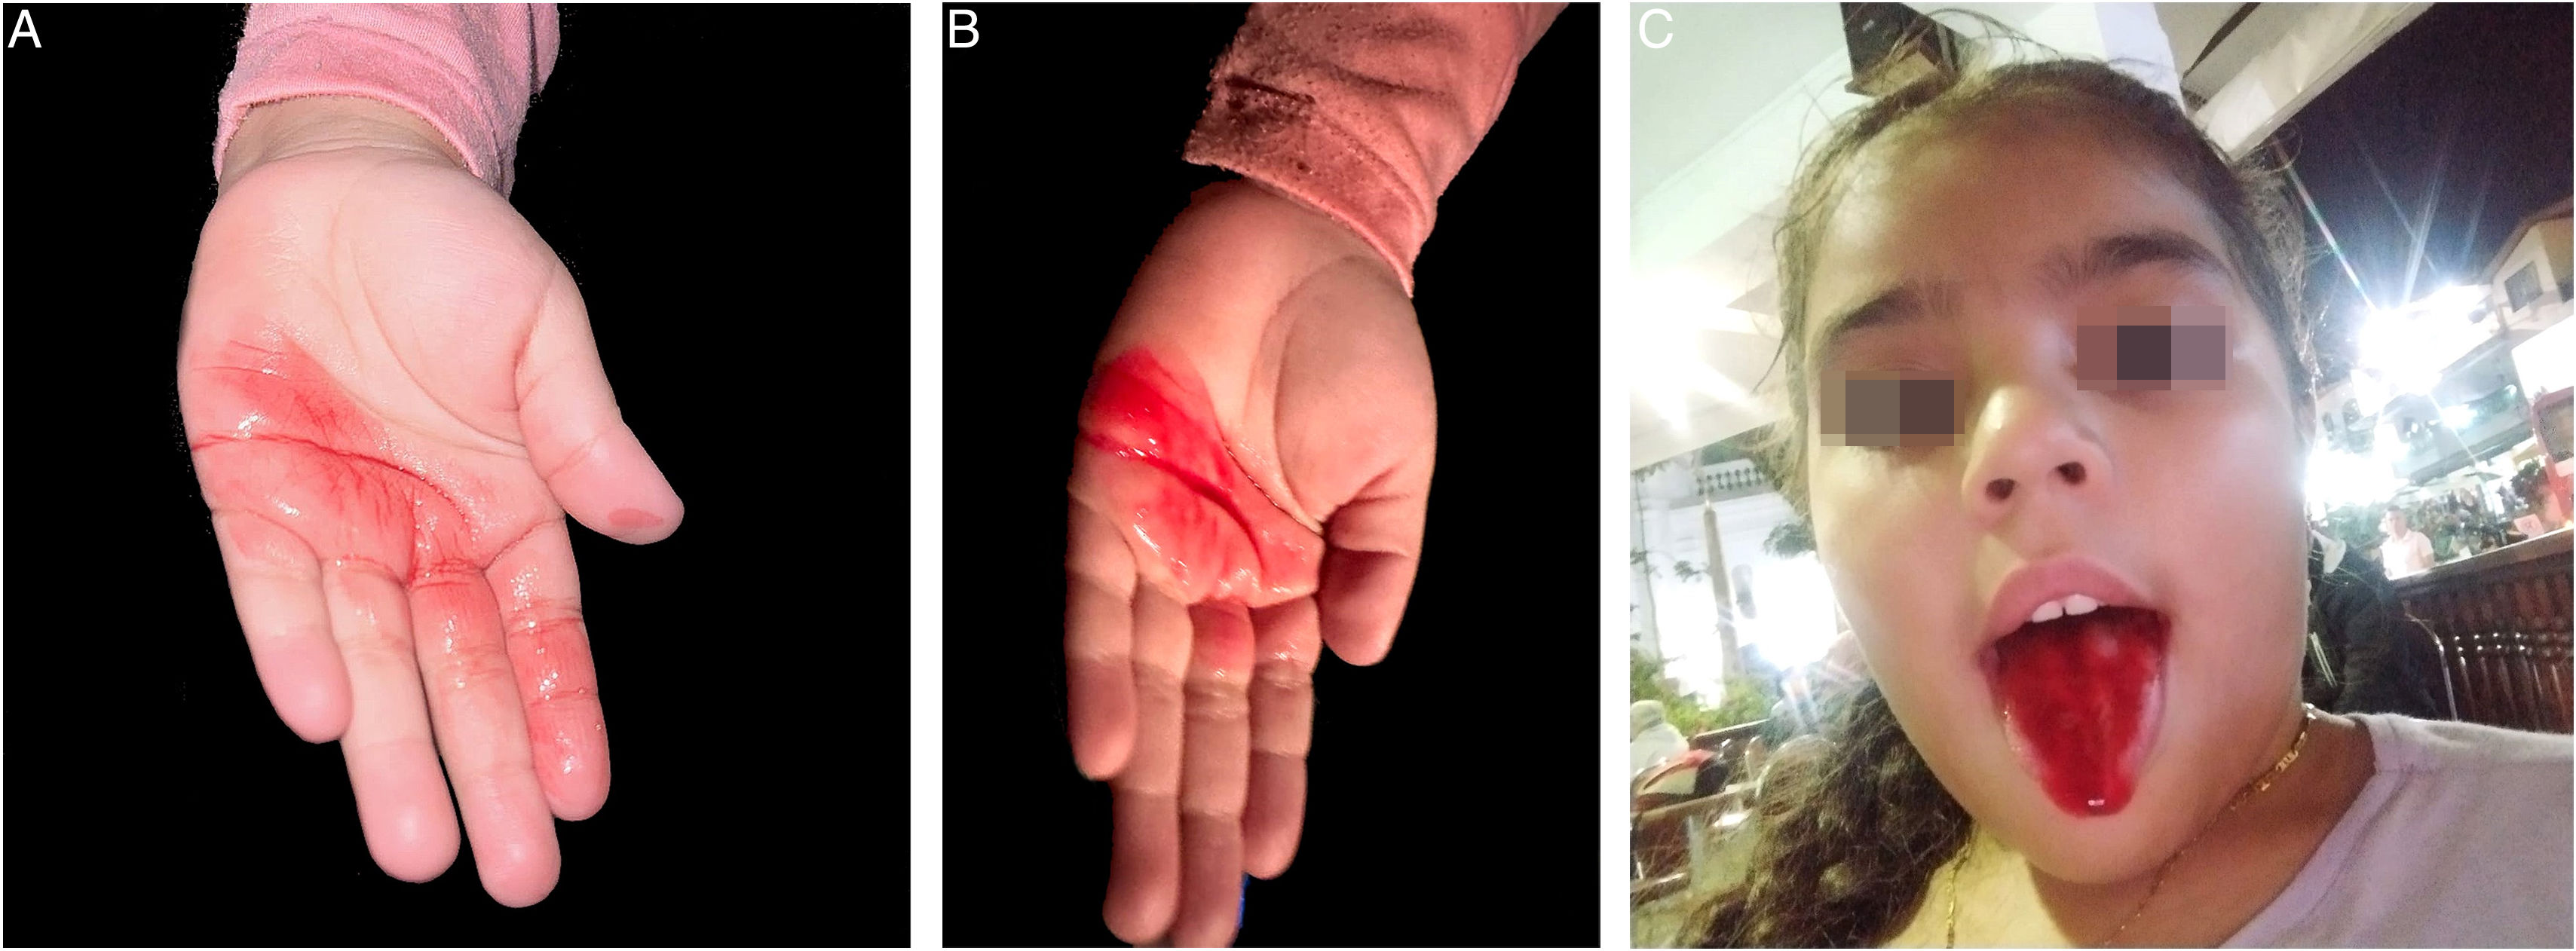
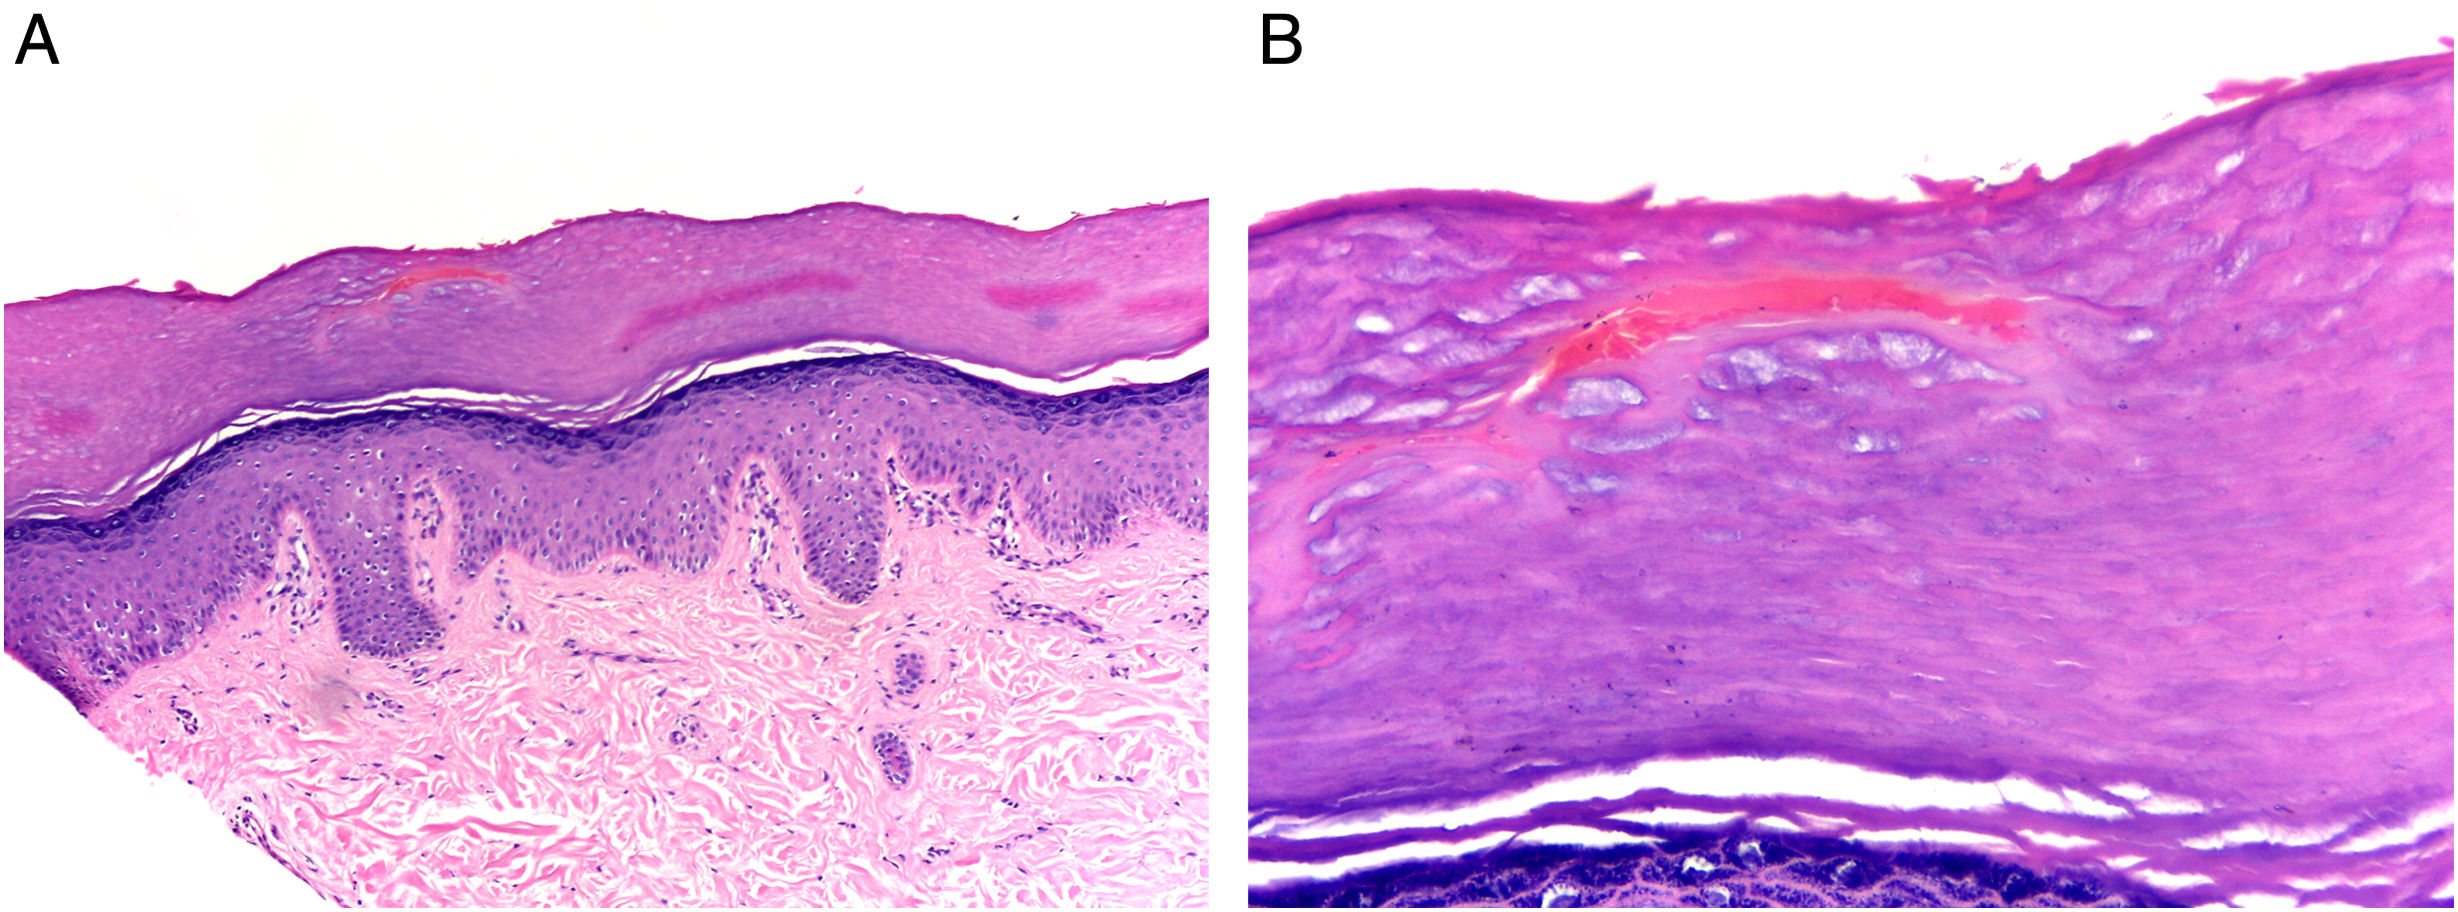
An 8-year-old girl with a personal history of asthma was brought by her mother to the dermatology clinic with a 10-day history of bloody sweating on her hands. She reported having had 3 episodes of sweating within half an hour and more than 10 during the night. In addition, she stated that on one occasion she had observed spontaneous bleeding on the tongue. A history of trauma to the affected areas was ruled out. Family history was explored, and the mother reported that, for several months, she had been undergoing divorce proceedings with the patient's father and that this had caused family turmoil. The mother provided photographs of the patient showing a red secretion with hematic characteristics on both palms and on the tongue (Fig. 1). On physical examination, the skin of both palms was intact. Blood tests showed a platelet count within normal limits and coagulation tests without abnormalities. Histological examination of a punch biopsy of palmar skin showed the presence of hematic material in the stratum corneum, with no evident damage to glandular or capillary structures (Fig. 2). A diagnosis of hematohidrosis was established, and treatment with metoprolol and psychological support was started, with marked improvement.


Hematohidrosis is a very rare clinical entity consisting of sweating blood. Very few cases have been reported in the literature. Its etiology is not well understood, but it is believed to be a systemic disease associated with hemorrhage in different locations, such as the rectum, vagina, or lacrimal gland. It has also been described in association with thrombotic thrombocytopenic purpura and psychiatric disorders.
Its association with extreme mental stress has been reported in 6 cases in men sentenced to execution and in other stressful situations, such as rape. Furthermore, the relationship between psychiatric disorders and bleeding has been observed in psychogenic purpura, in which the patient's own blood generates a hypersensitivity reaction and causes ecchymotic lesions.1 Altered psychological states have also been associated with hematohidrosis, such as disorders in relationships with family members and attachment bonds in pediatric patients, the need for recognition in adolescents, and anxiety in caregivers. Although its clinical signs may be dramatic, it is not a life-threatening disease.2
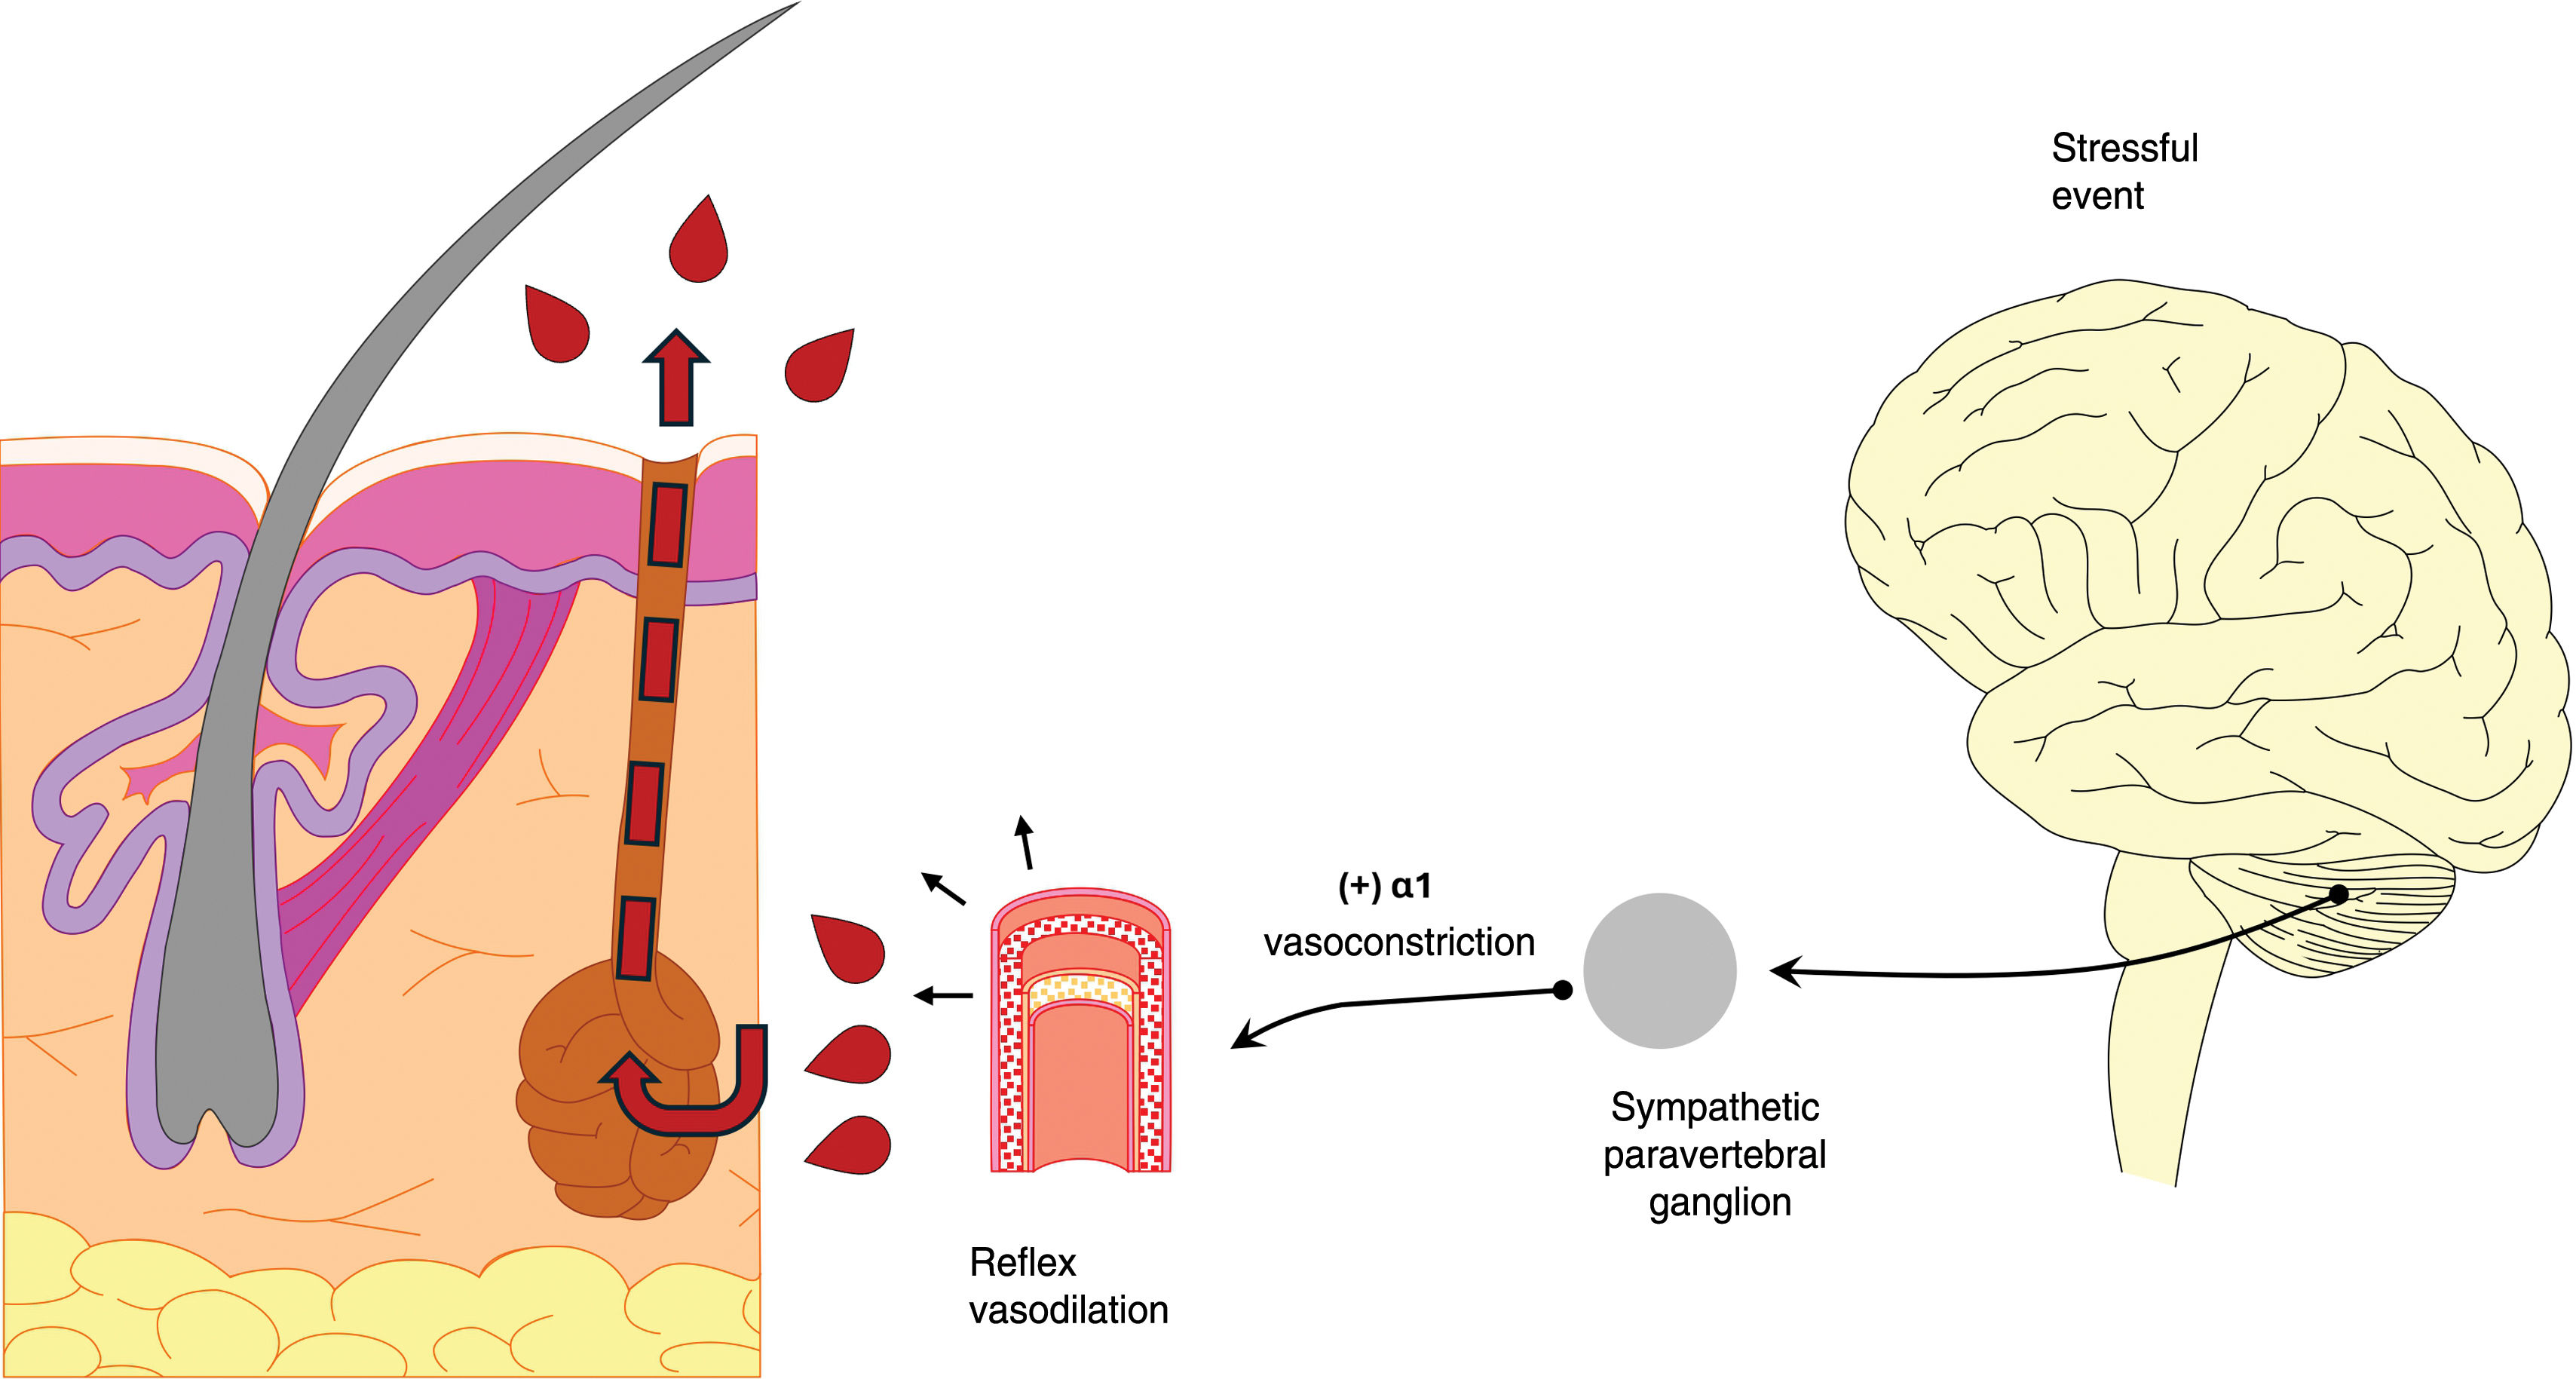
Several theories have been proposed to explain the pathophysiology of the disease. The essence of all of them is based on the fact that anxiety states activate the sympathetic nervous system, triggering a response that causes hemorrhage in blood vessels adjacent to the sweat glands. It has been proposed that blood vessels located around the sweat glands, which are arranged in a network, would experience increased pressure under stress conditions in response to sympathetic activity.3 This would lead to vessel contraction followed by dilation, resulting in micro-ruptures of the vessels. The extravasated blood would thus reach the sweat glands and be propelled, together with sweat, toward the epidermis (Fig. 3). The systemic effects that may appear secondary to hematohidrosis include asthenia and mild dehydration due to loss of sweat and blood.1

Anatomical arrangement at the level of the sweat gland, with blood vessels organized in a network. Under stress conditions, sympathetic activation occurs with an alpha-1 receptor response; pressure is generated and the vessels close to the gland contract, subsequently dilating and rupturing. The extravasated blood is propelled, together with sweat, toward the epidermis.
It has recently been described that there may be certain defects in the dermis that cause stromal weakness. This defect communicates with the vascular spaces in the dermis, dilating them and promoting rupture when blood flow increases,1,4 with blood exiting through follicular channels or directly onto the skin surface. A biopsy performed immediately after the episode could demonstrate these vascular spaces, since over time they may collapse and no longer be identifiable. The skin remains intact between bleeding episodes, although erythematous areas or vesicle formation may appear before sweating.5
For diagnosis of the disease, disorders such as hemorrhagic diathesis or other dermatological diseases that could explain the findings must be ruled out.2 Exploring family history and dynamics is an important part of the anamnesis in these patients, since, as mentioned above, this has been identified as a frequent trigger.6
This disorder should be differentiated from other alterations in sweating, such as chromhidrosis, in which sweat color is altered by the presence of substances such as lipofuscin, certain medications, or heavy metal poisoning.7 Pseudochromhidrosis is different, as the sweat is normal but becomes pigmented when it comes into contact with the skin. This occurs due to the presence of chemicals, most widely found in deodorants, or metabolic products of fungi present on the skin.8
Currently, no treatments have been shown to be effective, although in most reported cases, psychological and psychiatric support improves the episodes.1 Beta-blockers have been used to inhibit sympathetic activity, and local administration of adrenaline has been used to reduce vascular tone.2 Anxiolytics and antidepressants are also treatment options.9
Informed consentThe patient was examined in full compliance with the principles outlined in the Declaration of Helsinki. The authors certify that they obtained the appropriate informed consent forms, in which the patient consented to the inclusion of images and other clinical information. The patient understands that her name and initials will not be published and that efforts will be made to protect her identity; however, anonymity cannot be guaranteed.
Conflict of interestThe authors declare that they have no conflict of interest.




