




Nail dystrophy is a very common reason for consultation. When a positive fungal culture is found, it is approached as onychomycosis and treatment is prescribed to cover the isolated organism, but neither the underlying cause nor restoration of nail morphology is addressed. Triggering factors that should be considered when there is no therapeutic response include antifungal resistance, the presence of biofilms, the need for prophylaxis, foot morphology, mechanical nail alterations, inappropriate footwear, and undiagnosed inflammatory diseases, among others.1,2
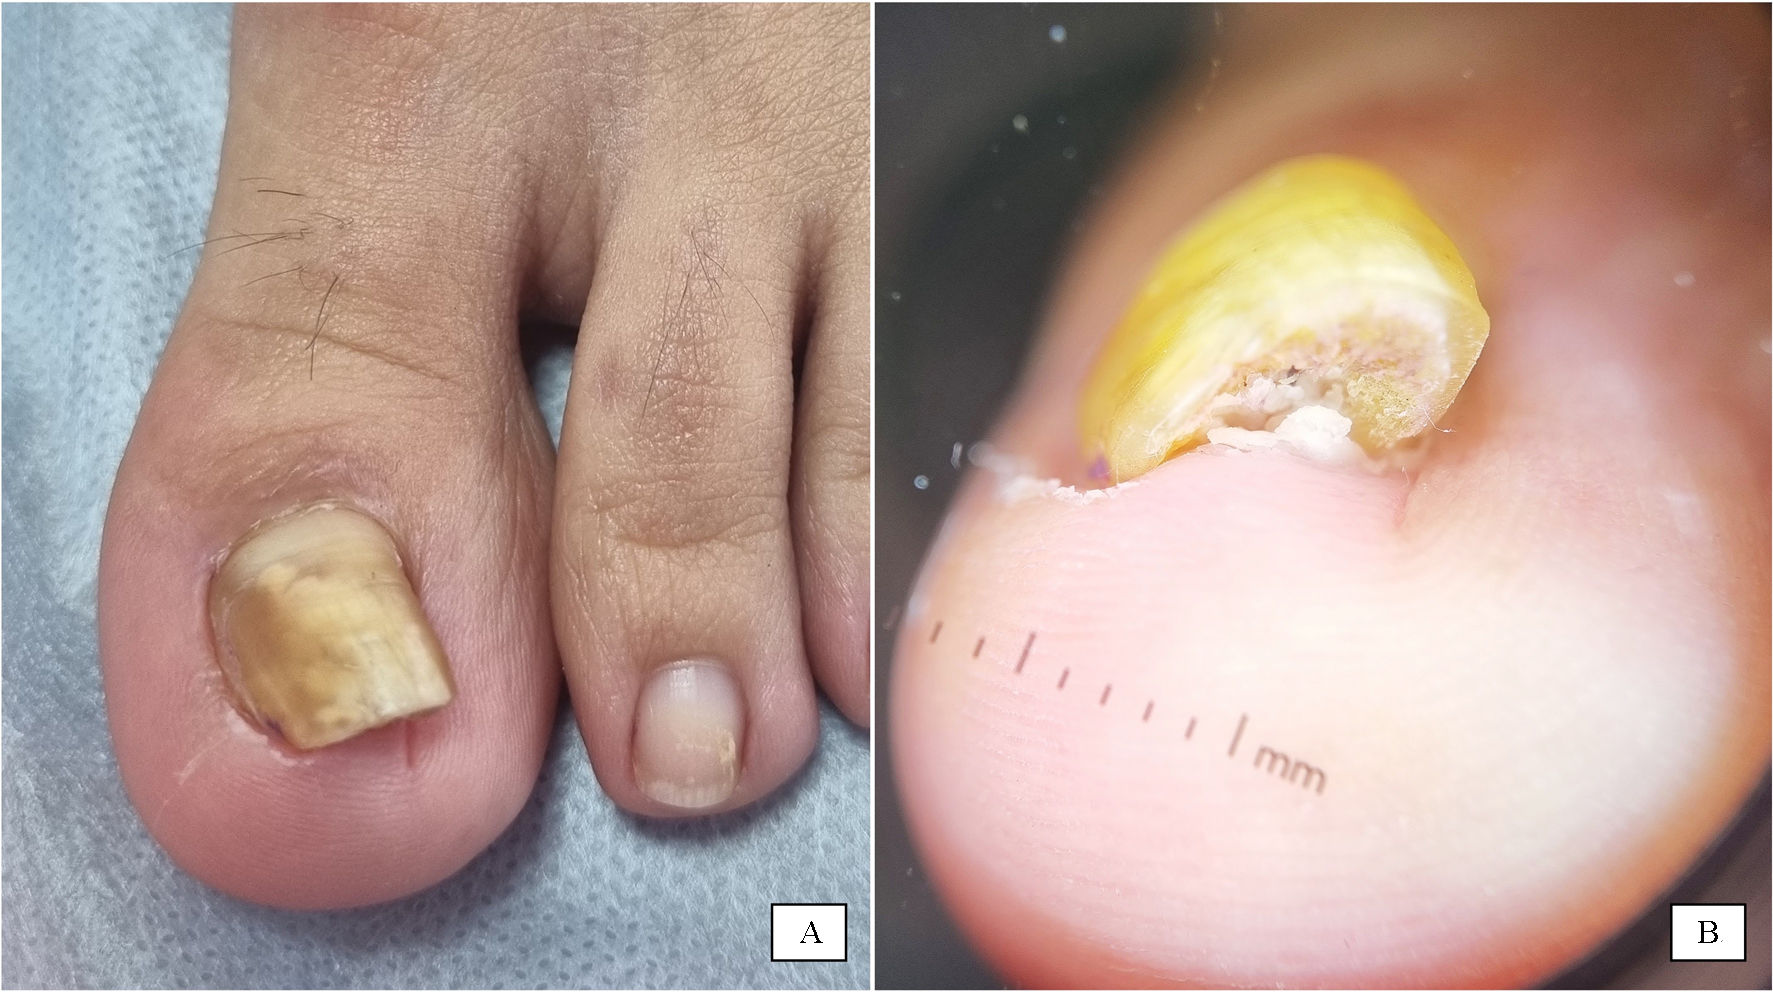
A 36-year-old woman with no relevant past medical history consulted because of a 3-year history of nail dystrophy of the left hallux secondary to blunt trauma. Trichophyton rubrum had been isolated in a nail-plate culture, and she had received numerous antifungal treatments, both topical—amorolfine, ciclopirox olamine, and terbinafine—and oral—fluconazole and itraconazole—without improvement. Examination revealed acquired deviation of the nail axis, white and yellowish leukonychia, dermatophytoma, onycholysis, onychauxis, and subungual hyperkeratosis (Fig. 1A, B), probably caused by loss of adhesion of the nail plate to the nail bed, which in turn was generated by the history of trauma and repetitive friction with footwear.

The situation illustrated here is quite common, and we know that controlling and addressing all the factors involved is not an easy task. Therefore, using our case as an example, we propose a comprehensive approach for restoring nail morphology.
Nail morphology depends on the complex interaction among the tissues that form the nail unit. This interaction can also be modified by external agents. When the hyponychium is affected by repeated microtrauma, excessive moisture, fungal infections, inflammatory diseases in this location, among other factors, the development of onycholysis—separation of the nail plate from the nail bed—and/or hyperkeratosis is favored, which in turn may damage the nail bed. When the nail bed is altered and becomes keratinized, the nail plate cannot adhere and grows detached, creating a perfect space for fungal and bacterial growth.3 A nail with onycholysis, subjected to gait dynamics and friction from inappropriate footwear, may deviate laterally, as observed in this case (Fig. 1).
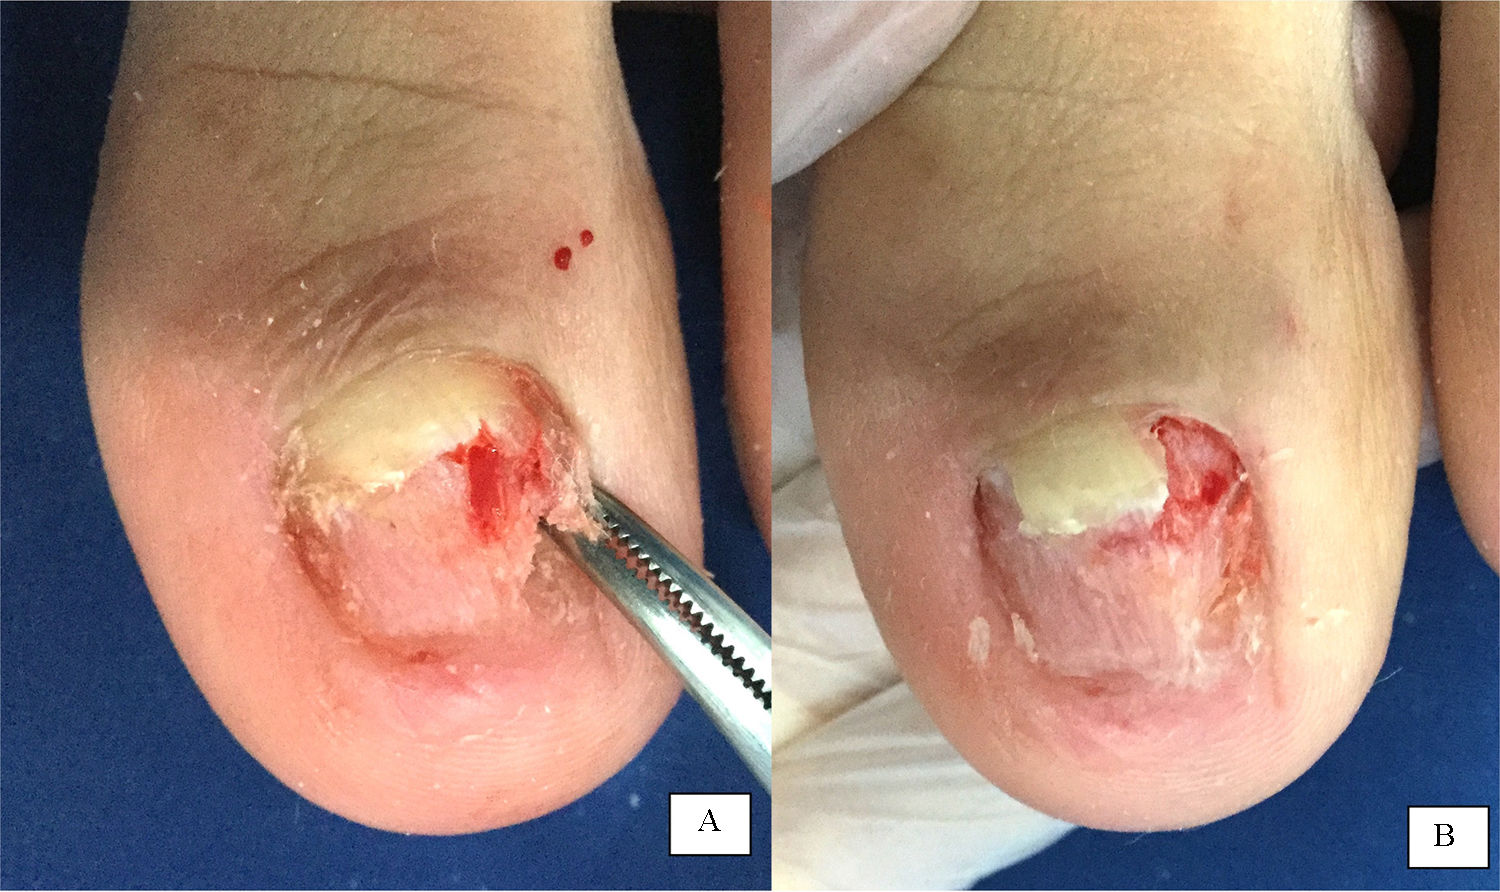
Restoration of nail-plate adhesion to the nail bed can be achieved by correcting onycholysis and hyperkeratosis. For this purpose, mechanical methods are available, including cutting the onycholytic band with nail nippers and abrasion of the nail plate and/or nail bed with a micromotor, and/or chemical methods, such as application of 40% urea.4–6 These methods aim to remove the dystrophic portion of the nail plate and prepare the nail bed so that the emerging plate can adhere correctly. In our case, the method selected was mechanical abrasion, since it allows removal of the desired portion of the nail plate, eradication of the biofilm, and recovery of the nail bed (Fig. 2).

(A) Nail bed after removal of the distal portion of the nail plate and hyperkeratosis. The forceps hold a fragment that is very adherent to the lateral fold and nail bed, causing its depression. (B) After removal of the lateral nail-plate fragment, the nail bed and a rectangle of healthy nail remain, which will serve as a guide for growth of the new nail plate.
In the absence of the nail plate, taping should be used to prevent the skin of the lateral and distal nail folds from interrupting, modifying, or deviating nail growth, and to prevent the nail bed from becoming keratinized, decreasing in size, and disappearing. This technique can be performed with various elastic materials, including kinesiology tape, dressings, and silicone toe caps.7 The material is chosen according to each case; the aim is to keep the periungual skin away from the nail bed. In our patient, distal and lateral taping was performed until complete nail growth.
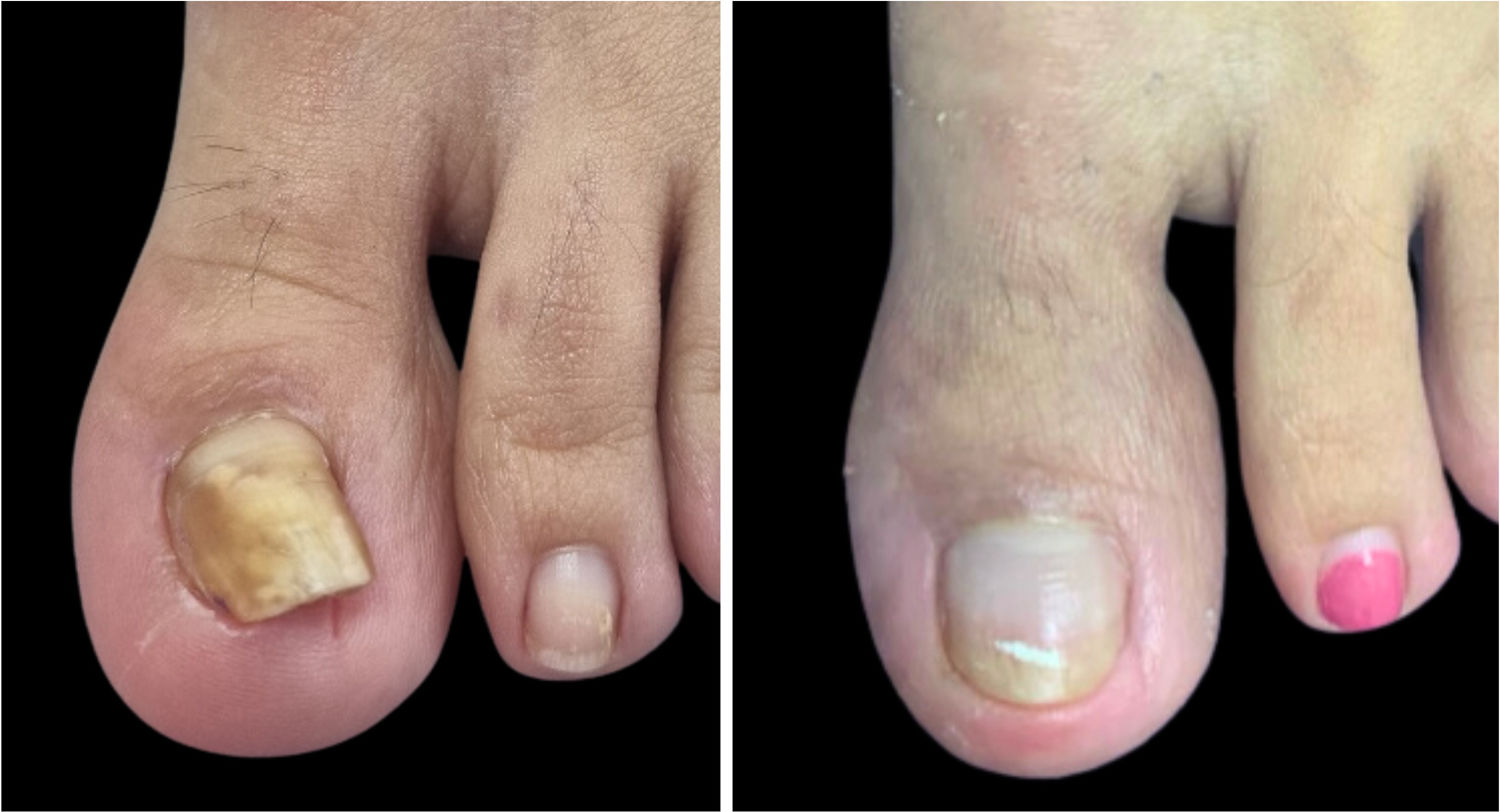
In our case, treatment was completed with 3 pulses of terbinafine at a dose of 500mg/day for 7 days, separated by 3 weeks, antibiofilm therapy with thymol and carvacrol,8 and topical antifungal therapy with 8% ciclopirox olamine in hydrosoluble lacquer at night for 24 weeks. After this period, the patient showed complete improvement (Fig. 3).

Once the nail plate has recovered, its adhesion must be ensured through adequate hydration. Preparations containing urea, lactic acid, linoleic acid, organic silicon, among others, are recommended.9 In individuals with permanent alterations of nail morphology due to surgery or previous trauma, or with high exposure to humid environments and chronic or recurrent onychomycosis, antifungal prophylaxis, avoidance of moisture, and appropriate footwear are recommended.10
This case shows how a comprehensive and methodical approach that addresses both the underlying cause and restoration of nail morphology is essential for the successful management of nail dystrophies.
Conflict of interestThe authors declare that they have no conflict of interest.




