






More than 7000 cases of cutaneous melanoma (CM) were diagnosed in Spain in 2023, and approximately 15% were stage II. Patients with stage IIB-C CM typically have lower survival rates than those with stage IIIB disease.
ObjectiveTo describe recurrence patterns and variations in healthcare resource utilization (HCRU) at disease progression in Spanish patients with stage II primary CM.
MethodsThis retrospective study included patients diagnosed with stage II CM (AJCC, 8th edition) between January 2013 and December 2017 at 11 Spanish hospitals. Disease characteristics, recurrence patterns, treatment after recurrence, survival outcomes, and HCRU were examined. Stages at diagnosis and time-to-event endpoints were also compared.
ResultsA total of 324 patients were included (52.2% male; median age, 64 years): 44.4% had stage IIA, 35.5% stage IIB, and 20.1% stage IIC disease. Ninety patients (27.8%) had at least 1 recurrence of CM; recurrence was lymphatic in 41.1%, hematogenous in 34.4%, and both in 20.0%. Most recurrent patients (54.4%) progressed to stage IV disease, mainly with lung metastases (70.1%). Eighty-one patients (90.0%) received treatment after recurrence: 58 (71.6%) received systemic treatment, 45 (55.6%) underwent surgery, and 25 (30.9%) received radiotherapy. Five-year recurrence-free survival was 74.5% for stage IIA, 62.6% for stage IIB, and 65.7% for stage IIC disease, with a significantly higher risk of recurrence in stages IIB/C versus IIA (HR, 1.52; 95%CI, 1.02–2.25; P=.039). After first recurrence, annual HCRU rates increased by 251%, with annual cost increases of €3018.68 for visits and €9428.73 for tests.
ConclusionsA substantial proportion of patients with stage II melanoma experience recurrence, often with distant metastases and a marked impact on healthcare resource utilization. These findings reinforce the need to optimize follow-up and advance adjuvant strategies.
The incidence of cutaneous melanoma (CM) has risen rapidly over the past few decades.1 In Spain, the incidence rate is approximately 15 cases per 100,000 inhabitants per year, and about 1000 deaths are reported annually, according to the Spanish Network of Cancer Registries (REDECAN) and the Spanish Society of Medical Oncology (SEOM).2
Most patients (approximately 85%) are diagnosed with localized melanoma, which can be managed by resection of the primary tumor with sentinel lymph node biopsy for stages IB and higher according to the American Joint Committee on Cancer (AJCC), 8th edition.3 However, 25–35% of these patients will develop recurrence, with approximately 50% occurring in regional lymph nodes, 20% as local recurrences, and 30% as distant recurrences.3
Although stage II melanoma represents localized disease, it is associated with a greater absolute number of eventual deaths than stages III and IV because of its much higher incidence. In addition, stages IIB and IIC are associated with worse prognosis than stages IIIA and IIIB, respectively.4 Prospective data show 5-year recurrence-free survival (RFS) rates of 54.7% for stage IIB and 26.5% for stage IIC disease.5 Retrospective analyses report slightly higher RFS rates of 64.4% and 41.5% for stages IIB and IIC, respectively.6 Comparisons between stage II and stage III subgroups should be interpreted with caution, because melanoma staging does not always follow a linear prognostic progression. For instance, stage IIB may have worse outcomes than stage IIIA, and stage IIC may have poorer prognosis than stage IIIB.7
Over the last decade, immune and targeted therapies have significantly improved survival in patients with metastatic melanoma.8 As patients with advanced disease live longer, locoregional control has become increasingly important. While surveillance guidelines and adjuvant therapy options are well established for stage III melanoma, follow-up protocols for stage II disease remain inconsistent, with no standardized intervals, imaging recommendations, or treatment strategies. Recently, adjuvant nivolumab and pembrolizumab have been shown to improve RFS in patients with resected stage IIB/C melanoma, leading to approval by the US Food and Drug Administration and the European Medicines Agency.9,10 However, further research is needed to guide treatment and monitoring in this population and to identify biomarkers that may support personalized decision-making. Clear guidance for monitoring patients with stage II CM is lacking, mainly because of limited research on recurrence patterns in this group. Understanding these patterns is essential for developing effective surveillance strategies and may require updates to current substage-specific guidelines.
In this context, the METHEOR study was designed to explore recurrence patterns in stage II cutaneous melanoma and to describe healthcare resource utilization in real-world clinical practice in Spain.
MethodsStudy design and patientsMETHEOR was a multicenter, retrospective, observational study conducted at 11 Spanish hospitals in accordance with the Declaration of Helsinki and national regulations. The appropriate ethics committee (Instituto Valenciano de Oncología [IVO]; reference 03/22) approved the study and granted a waiver of informed consent.
Eligible patients were aged 18 years or older and had primary pathologic stage II CM (AJCC, 8th edition) diagnosed between January 2013 and December 2017, allowing a minimum follow-up of 5 years. Patients with vascular invasion or incomplete excision of the primary tumor were excluded. Vascular invasion was included as an exclusion criterion by the research team because it was considered a sign of lymphatic spread, despite not being included in the latest AJCC classification; thus, only patients without evidence of this type of dissemination were included.
The primary endpoint was recurrence-free survival, defined as the time from primary tumor excision (index date) to first recurrence or death. Recurrence was defined as lymphatic dissemination (locoregional skin and lymph nodes) or hematogenous metastasis (distant organs). Secondary endpoints included overall survival (OS), defined as time from index date to death or last contact; melanoma-specific survival (MSS), defined as time from index date to death due to melanoma; and distant metastasis-free survival (DMFS), defined as time from index date to first distant metastasis, death, or last contact. Additional secondary endpoints were to describe clinical characteristics, identify clinical factors associated with time-to-event outcomes, and explore HCRU related to stage II CM.
Statistical considerationsThe sample size calculation was based on a precision of 5.0% with a 95% confidence interval for a reference value of 70% for 5-year recurrence of stage II CM,5,6,11,12 assuming a 5% missing data rate, resulting in a target sample size of 340 patients.
Baseline demographic variables (age, sex, race/ethnicity) and clinicopathologic variables (tumor location, thickness, ulceration, histologic subtype, mitotic rate, histologic regression, tumor-infiltrating lymphocytes, and treatment) were collected to explore associations with outcomes. Healthcare resource utilization was assessed through hospital admissions, surgical procedures (e.g., lymph node biopsy, recurrence resections, metastatic procedures), healthcare visits, and laboratory tests (complete blood count, biochemistry, coagulation).
Data collected from health records included demographics; melanoma characteristics (tumor thickness, primary site, ulceration, regression, mitotic rate, histologic subtype, lymphocytic infiltration); Eastern Cooperative Oncology Group (ECOG) performance status; Charlson Comorbidity Index13; primary treatment; recurrence details (stage, site, subsequent therapy); survival status; and follow-up. HCRU data included diagnostic tests, hospitalizations, outpatient consultations, day hospital visits, and emergency visits. Categorical variables were described as frequencies and percentages, and continuous variables as means±standard deviation, medians, and ranges. Stage comparisons at diagnosis were performed using Fisher exact test. Time-to-event endpoints were analyzed using the Kaplan–Meier method and Cox proportional hazards models, with results presented as hazard ratios with 95%CI and P values. Survival outcomes were analyzed and compared for stages IIA, IIB, and IIC. To assess clinical variability, survival outcomes for stage IIA CM were contrasted with those for stages IIB/C. Five-year RFS, OS, MSS, and DMFS were also estimated for the entire population, for patients with stages IIA, IIB, and IIC, and for the combined IIB/C group.
A Cox regression model was used to evaluate the association between demographic and clinical factors and survival outcomes in stage IIA and IIB/C CM. Variables with P<.20 in bivariate analysis were included in the multivariable model.
Unit costs were obtained from the Spanish health database eSalud.14 When multiple costs were identified, the mean was used. Radiotherapy costs were based on 5 sessions per week for up to 30 days; longer treatments were considered inconsistent. Surgery costs were differentiated by lymph node resection versus non-lymph node resection and were based on a 2017 study,15 adjusted to the 2024 consumer price index (CPI).16
Missing data were excluded from analyses. A significance level of .05 was used for statistical testing. IBM SPSS Statistics version 29.0 (IBM Corp) was used for statistical analysis, and Stata version 14.0 (StataCorp) was used for the cost analysis.
ResultsStage at diagnosis and patient characteristicsA total of 324 patients were included. Median age (IQR) was 64 (51–73) years, and 169 patients (52.2%) were male. Ulceration was present in 194 patients (59.9%). A total of 102 patients (31.5%) had Breslow thickness >2mm, and 271 patients (83.6%) had a mitotic rate >5/mm2. Most tumors were nodular melanoma (134 patients [41.4%]) or superficial spreading melanoma (108 patients [33.3%]). Overall, 144 patients (44.4%) were classified as stage IIA, 115 (35.5%) as stage IIB, and 65 (20.1%) as stage IIC (Table 1).
Baseline patient characteristics (N=324).
| Patient characteristics | Value |
|---|---|
| Age, years, median (IQR) | 64.0 (51.0–73.0) |
| Male sex, n (%) | 169 (52.2) |
| White ethnicity, n (%) | 323 (99.7) |
| Tumor location, n (%) | |
| Trunk | 128 (39.5) |
| Lower extremities | 61 (18.8) |
| Head and neck | 55 (17.0) |
| Upper extremities | 48 (14.8) |
| Acral | 32 (9.9) |
| Breslow thickness, mm, n (%) | |
| >1.0–2.0 | 53 (16.4) |
| >2.0–4.0 | 176 (54.3) |
| >4.0 | 95 (29.3) |
| Mitoses/mm2, n (%) | |
| <1 | 26 (8.0) |
| 1–2 | 98 (30.2) |
| 3–5 | 94 (29.0) |
| >5 | 102 (31.5) |
| Missing | 4 (1.2) |
| Ulceration present, n (%) | 194 (59.9) |
| Signs of regression, n (%) | 39 (12.0) |
| Tumor-infiltrating lymphocytes, n (%) | |
| Absent | 44 (13.6) |
| Mild/moderate | 158 (48.8) |
| Intense | 48 (14.8) |
| Missing | 74 (22.8) |
| ECOG performance status 0–1a, n (%) | 113 (99.1) |
| Stage II CM substage (AJCC, 8th edition), n (%) | |
| IIA | 144 (44.4) |
| IIB | 115 (35.5) |
| IIC | 65 (20.1) |
| Histologic subtype, n (%) | |
| Nodular | 134 (41.4) |
| Superficial spreading | 108 (33.3) |
| Acral lentiginous | 29 (9.0) |
| Lentigo maligna | 14 (4.3) |
| Desmoplastic | 8 (2.5) |
| Spitzoid | 1 (0.3) |
| Other | 30 (9.3) |
| Charlson Comorbidity Index, median (IQR) | 2 (1–4) |
| <6, n (%) | 293 (90.4) |
| ≥6, n (%) | 30 (9.3) |
| Missing, n (%) | 1 (0.3) |
| Primary CM treatment, in addition to surgery, n (%) | |
| Pharmacologic treatment | 28 (8.6) |
| Radiotherapy | 3 (0.9) |
AJCC, American Joint Committee on Cancer; CM, cutaneous melanoma; ECOG, Eastern Cooperative Oncology Group; IQR, interquartile range.
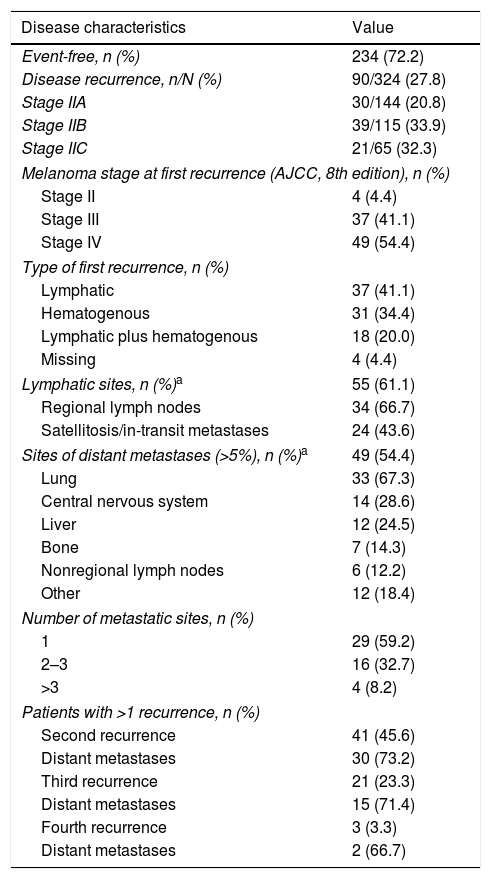
After a median follow-up of 69 months (IQR, 53–87), 90 patients (27.8%) experienced at least 1 recurrence. Of these, 37 (41.1%) had lymphatic dissemination, including 25 (66.7%) with regional lymph node involvement and 16 (43.6%) with satellite or in-transit metastases. Hematogenous dissemination to distant organs was observed in 31 patients (34.4%), whereas 18 patients (20.0%) had both lymphatic and hematogenous dissemination. Type of dissemination was not reported for 4 patients (4.4%) (Table 2).
Disease characteristics at first recurrence (N=90).
| Disease characteristics | Value |
|---|---|
| Event-free, n (%) | 234 (72.2) |
| Disease recurrence, n/N (%) | 90/324 (27.8) |
| Stage IIA | 30/144 (20.8) |
| Stage IIB | 39/115 (33.9) |
| Stage IIC | 21/65 (32.3) |
| Melanoma stage at first recurrence (AJCC, 8th edition), n (%) | |
| Stage II | 4 (4.4) |
| Stage III | 37 (41.1) |
| Stage IV | 49 (54.4) |
| Type of first recurrence, n (%) | |
| Lymphatic | 37 (41.1) |
| Hematogenous | 31 (34.4) |
| Lymphatic plus hematogenous | 18 (20.0) |
| Missing | 4 (4.4) |
| Lymphatic sites, n (%)a | 55 (61.1) |
| Regional lymph nodes | 34 (66.7) |
| Satellitosis/in-transit metastases | 24 (43.6) |
| Sites of distant metastases (>5%), n (%)a | 49 (54.4) |
| Lung | 33 (67.3) |
| Central nervous system | 14 (28.6) |
| Liver | 12 (24.5) |
| Bone | 7 (14.3) |
| Nonregional lymph nodes | 6 (12.2) |
| Other | 12 (18.4) |
| Number of metastatic sites, n (%) | |
| 1 | 29 (59.2) |
| 2–3 | 16 (32.7) |
| >3 | 4 (8.2) |
| Patients with >1 recurrence, n (%) | |
| Second recurrence | 41 (45.6) |
| Distant metastases | 30 (73.2) |
| Third recurrence | 21 (23.3) |
| Distant metastases | 15 (71.4) |
| Fourth recurrence | 3 (3.3) |
| Distant metastases | 2 (66.7) |
By stage at diagnosis, median follow-up was 71.5 months (IQR, 52.8–89.1) for stage IIA, 67.2 months (IQR, 53.4–87.0) for stage IIB, and 63.9 months (IQR, 51.3–83.2) for stage IIC disease. Recurrence occurred in 30 of 144 patients (20.8%) with stage IIA, 39 of 115 (33.9%) with stage IIB, and 21 of 65 (32.3%) with stage IIC disease (Table 2).
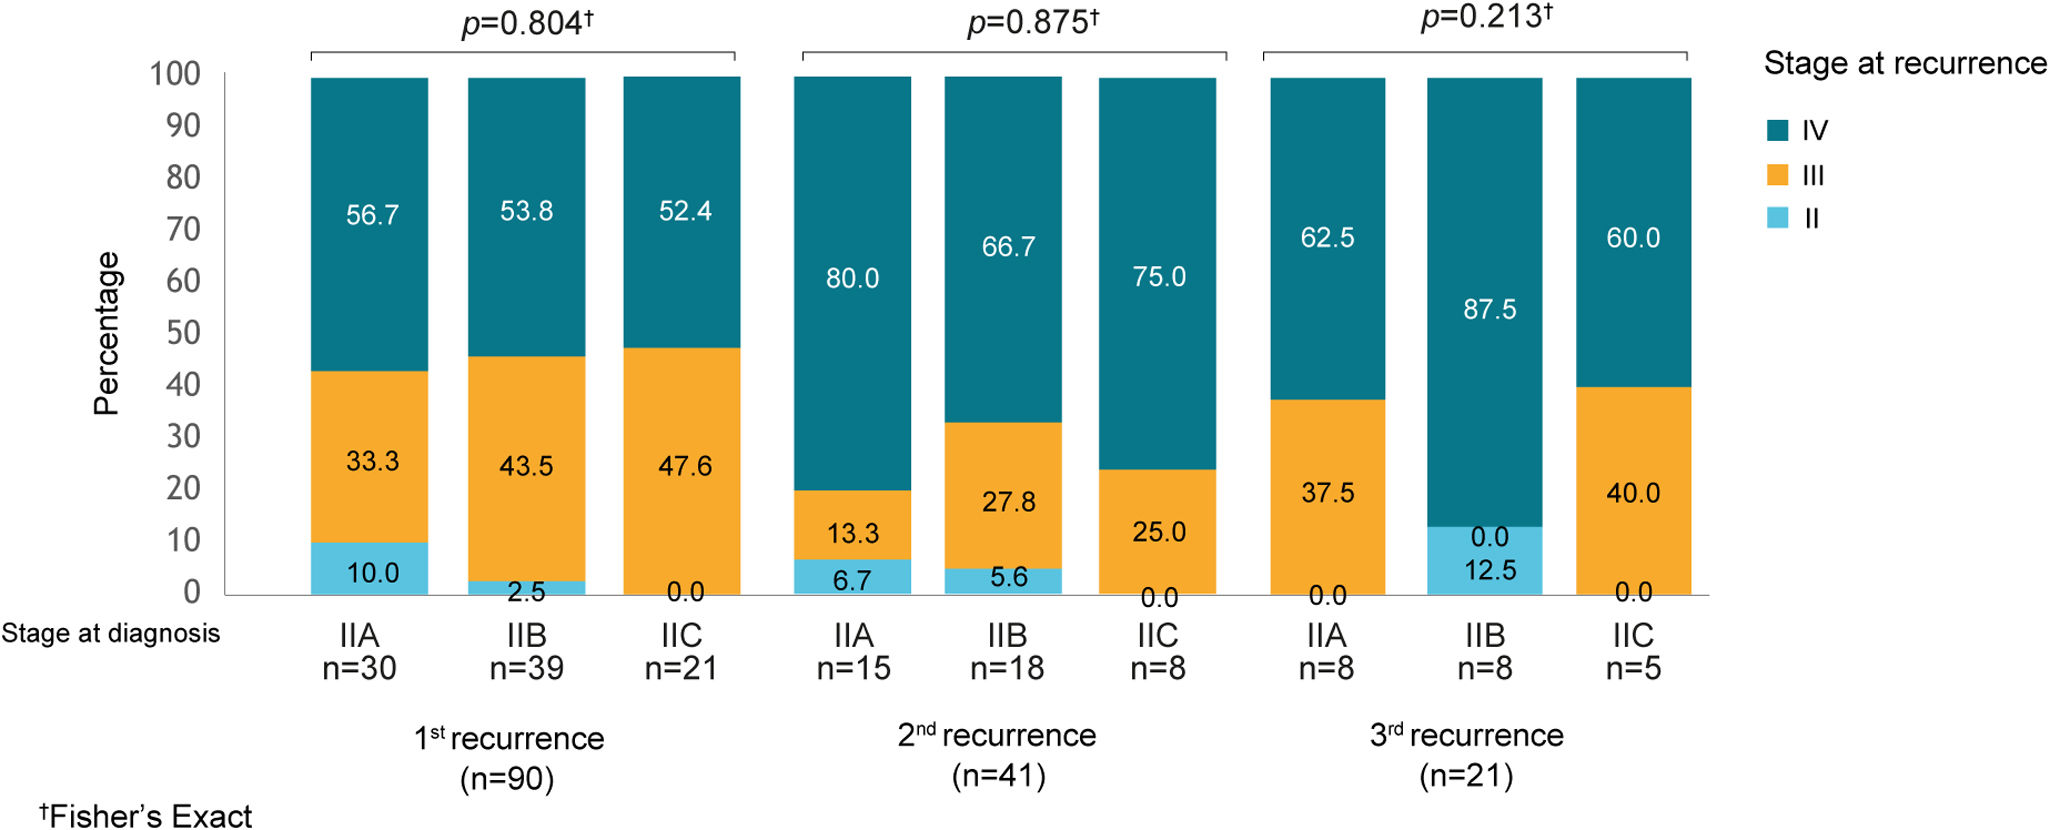
Patients most frequently progressed to stage IV disease (49 of 90 [54.4%]). Among those with distant recurrence, 32 of 49 (65.3%) had metastases in 2–3 distinct sites, most commonly the lung (33 of 49 [67.3%]), followed by the brain (14 of 49 [28.6%]) and liver (12 of 49 [24.5%]). Forty-one patients (45.6%) had a second or subsequent recurrence. Of these, 30 of 41 (73.2%) were stage IV at second recurrence, and 15 of 21 (71.4%) were stage IV at third recurrence (Table 2). Recurrence patterns were similar across the 3 stages (P1st=.804; P2nd=.875; P3rd=.213) (Fig. 1).
Treatment patterns at CM recurrence
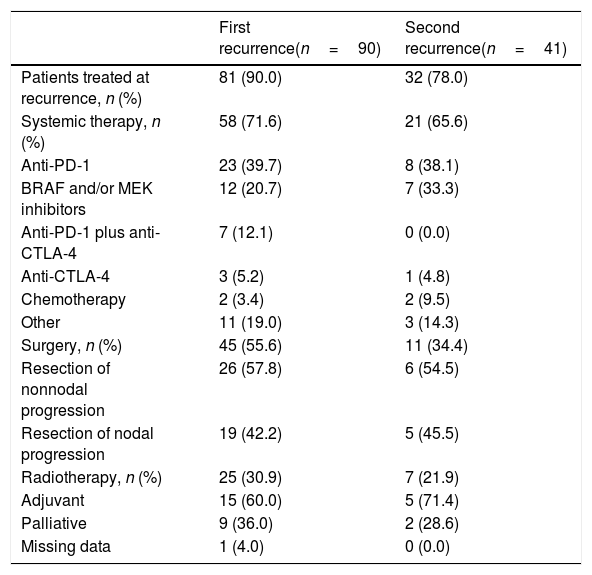
Of the 90 patients with recurrence, 81 (90.0%) received treatment after first recurrence. Of these, 58 (71.6%) received systemic treatment, mainly anti-PD-1 therapy (23 [39.7%]), BRAF/MEK inhibitors (12 [20.7%]), and anti-PD-1/CTLA-4 combinations (7 [12.1%]). Surgery was performed in 45 patients (55.6%), including 26 (57.8%) for nonnodal progression and 19 (42.2%) for nodal progression, and 25 patients (30.9%) received radiotherapy, including 9 (36.0%) with palliative intent (Table 3). Treatment patterns among the 32 patients treated for a second relapse were similar (Table 3).
Treatment patterns at CM recurrence.
| First recurrence(n=90) | Second recurrence(n=41) | |
|---|---|---|
| Patients treated at recurrence, n (%) | 81 (90.0) | 32 (78.0) |
| Systemic therapy, n (%) | 58 (71.6) | 21 (65.6) |
| Anti-PD-1 | 23 (39.7) | 8 (38.1) |
| BRAF and/or MEK inhibitors | 12 (20.7) | 7 (33.3) |
| Anti-PD-1 plus anti-CTLA-4 | 7 (12.1) | 0 (0.0) |
| Anti-CTLA-4 | 3 (5.2) | 1 (4.8) |
| Chemotherapy | 2 (3.4) | 2 (9.5) |
| Other | 11 (19.0) | 3 (14.3) |
| Surgery, n (%) | 45 (55.6) | 11 (34.4) |
| Resection of nonnodal progression | 26 (57.8) | 6 (54.5) |
| Resection of nodal progression | 19 (42.2) | 5 (45.5) |
| Radiotherapy, n (%) | 25 (30.9) | 7 (21.9) |
| Adjuvant | 15 (60.0) | 5 (71.4) |
| Palliative | 9 (36.0) | 2 (28.6) |
| Missing data | 1 (4.0) | 0 (0.0) |
BRAF, B-Raf proto-oncogene; CM, cutaneous melanoma; CTLA-4, cytotoxic T-lymphocyte-associated protein 4; MEK, mitogen-activated protein kinase kinase; PD-1, programmed cell death protein 1.
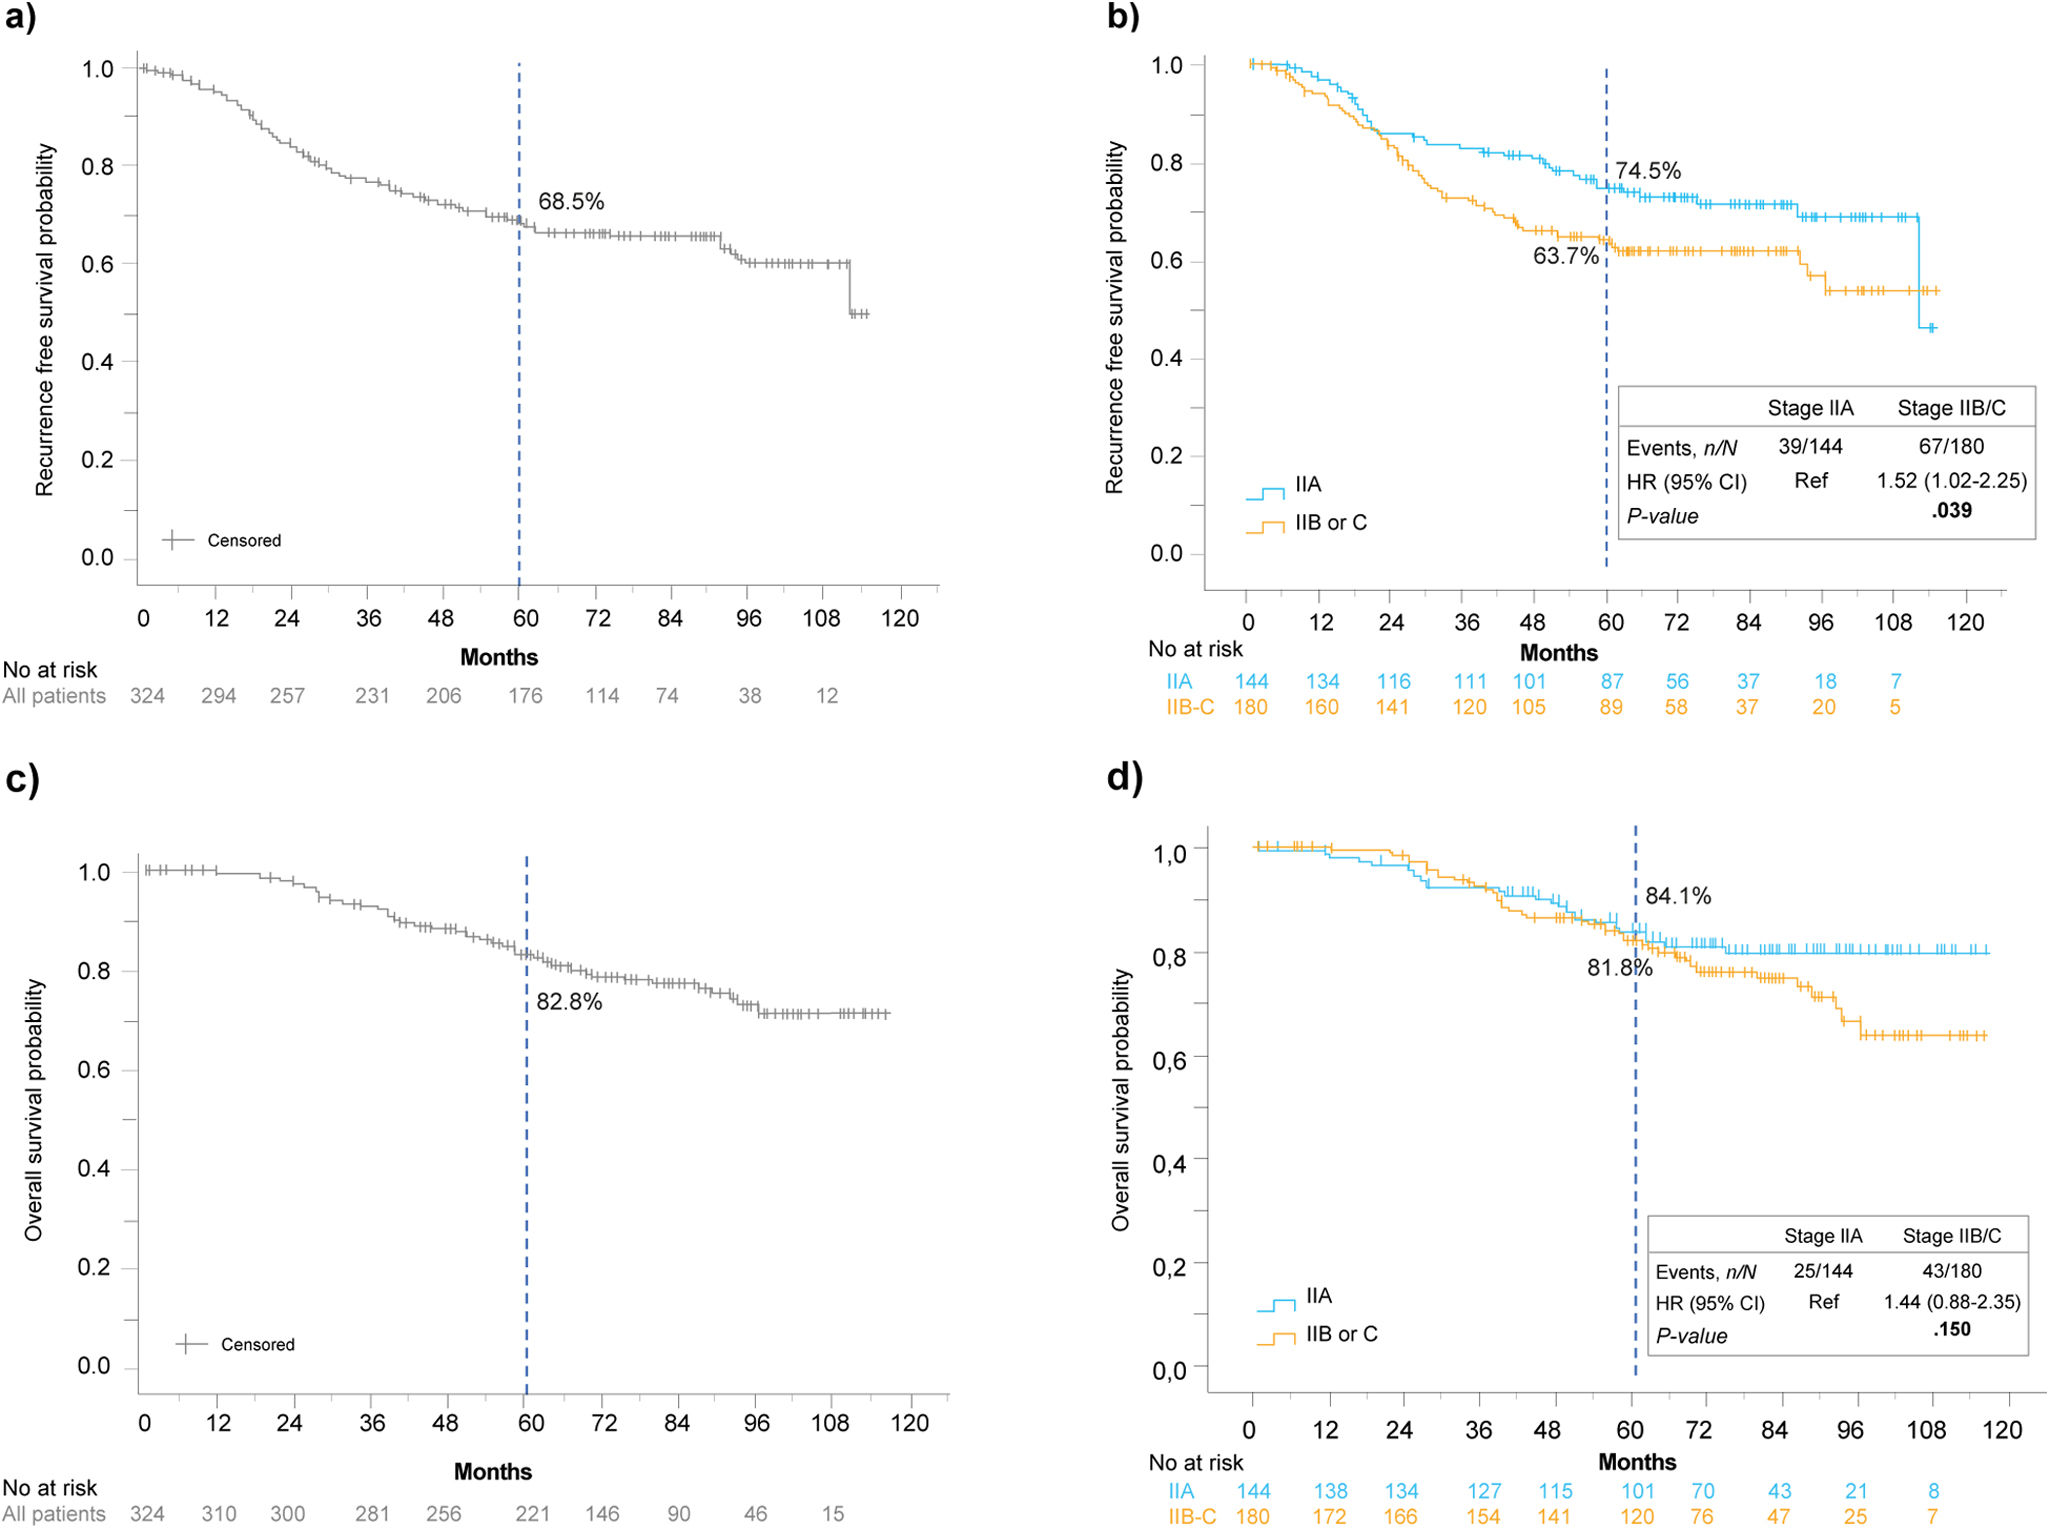
Overall 5-year RFS was 68.5% (Fig. 2A), specifically 74.5% for stage IIA, 62.6% for stage IIB, and 65.7% for stage IIC disease. Risk of recurrence was significantly higher for stages IIB/C than for stage IIA (HR, 1.52; 95%CI, 1.02–2.25; P=.039) (Fig. 2B). Individually, stage IIB had a significantly higher risk (HR, 1.56; 95%CI, 1.01–2.39; P=.043), whereas stage IIC did not reach significance (HR, 1.44; 95%CI, 0.85–2.42; P=.175) (Supplementary Fig. 1A).

The 5-year OS for all patients was 82.8% (Fig. 2C), specifically 84.1% for stage IIA, 80.9% for stage IIB, and 83.3% for stage IIC disease (Supplementary Fig. 1B). For stages IIB/C, the risk of death was HR, 1.44; 95%CI, 0.88–2.35; P=.150. Stage IIB (HR, 1.49; 95%CI, 0.87–2.54; P=.145) and stage IIC (HR, 1.34; 95%CI, 0.70–2.58; P=.382) had higher but nonsignificant risk compared with stage IIA (Supplementary Fig. 1B). At the end of follow-up, 68 patients (21.0%) had died: 45 (66.2%) from melanoma, 18 (26.5%) from other causes, and 5 (7.4%) from unknown causes.
Five-year MSS and DMFS were 87.6% and 73.5%, respectively, for the overall population (Supplementary Fig. 2A and D), 90.8% and 77.2% for stage IIA, 84.4% and 68.7% for stage IIB, and 86.2% and 73.7% for stage IIC disease, respectively (Supplementary Fig. 2C and F). For stage IIB/C, melanoma-specific mortality risk was HR, 1.66; 95%CI, 0.90–3.10; P=.106, and risk of distant metastasis was HR, 1.47; 95%CI, 0.96–2.24; P=.076 (Supplementary Fig. 2B and E).
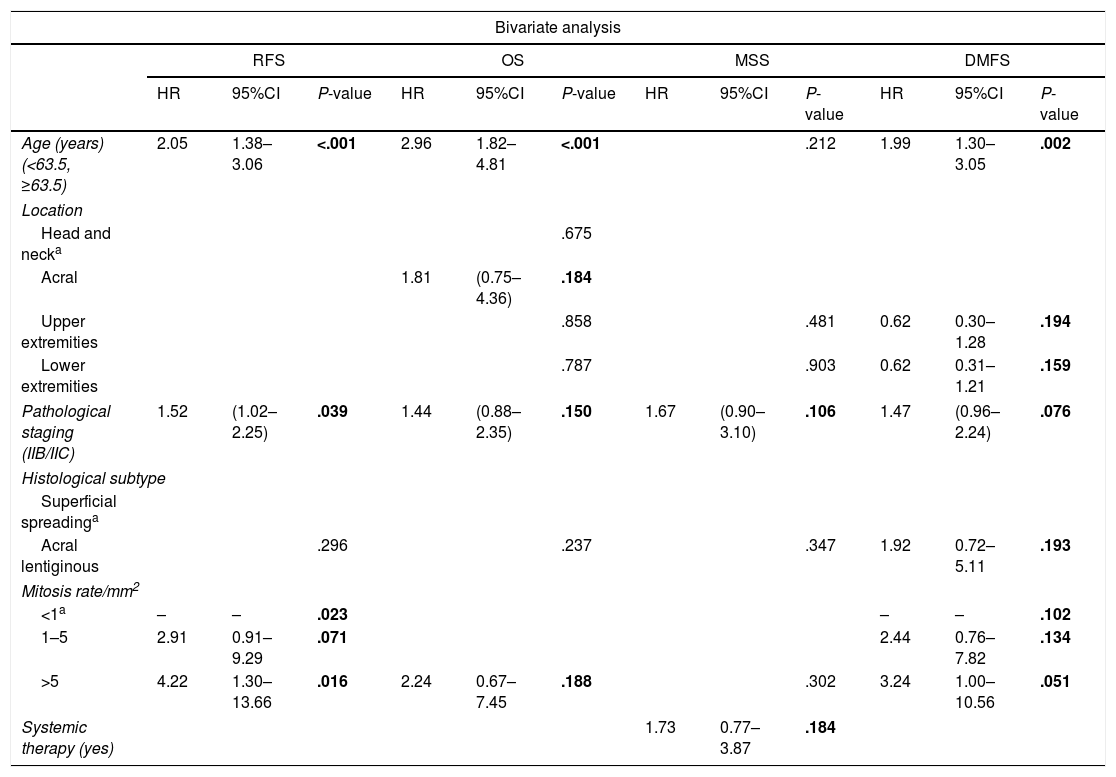
Cox regression analysisUnivariable Cox proportional hazards analysis showed that age, pathologic stage IIB/IIC, and mitotic rate >5/mm2 were associated with shorter RFS; age and pathologic stage IIB/IIC were associated with shorter DMFS; and age was associated with shorter OS. No factor was associated with MSS. Multivariable analysis revealed that age and mitotic rate greater than 5/mm2 were independent predictors of RFS, and age was an independent predictor of OS and DMFS (P<.02 for all) (Table 4).
Cox proportional hazard models evaluating clinical factors associated with survival outcomes.
| Bivariate analysis | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| RFS | OS | MSS | DMFS | |||||||||
| HR | 95%CI | P-value | HR | 95%CI | P-value | HR | 95%CI | P-value | HR | 95%CI | P-value | |
| Age (years) (<63.5, ≥63.5) | 2.05 | 1.38–3.06 | <.001 | 2.96 | 1.82–4.81 | <.001 | .212 | 1.99 | 1.30–3.05 | .002 | ||
| Location | ||||||||||||
| Head and necka | .675 | |||||||||||
| Acral | 1.81 | (0.75–4.36) | .184 | |||||||||
| Upper extremities | .858 | .481 | 0.62 | 0.30–1.28 | .194 | |||||||
| Lower extremities | .787 | .903 | 0.62 | 0.31–1.21 | .159 | |||||||
| Pathological staging (IIB/IIC) | 1.52 | (1.02–2.25) | .039 | 1.44 | (0.88–2.35) | .150 | 1.67 | (0.90–3.10) | .106 | 1.47 | (0.96–2.24) | .076 |
| Histological subtype | ||||||||||||
| Superficial spreadinga | ||||||||||||
| Acral lentiginous | .296 | .237 | .347 | 1.92 | 0.72–5.11 | .193 | ||||||
| Mitosis rate/mm2 | ||||||||||||
| <1a | – | – | .023 | – | – | .102 | ||||||
| 1–5 | 2.91 | 0.91–9.29 | .071 | 2.44 | 0.76–7.82 | .134 | ||||||
| >5 | 4.22 | 1.30–13.66 | .016 | 2.24 | 0.67–7.45 | .188 | .302 | 3.24 | 1.00–10.56 | .051 | ||
| Systemic therapy (yes) | 1.73 | 0.77–3.87 | .184 | |||||||||
| Multivariate analysis | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| RFS | OS | MSS | DMFS | |||||||||
| HR | 95%CI | P-value | HR | 95%CI | P-value | HR | 95%CI | P-value | HR | 95%CI | P-value | |
| Age (years) (<63.5, ≥63.5) | 2.04 | 1.35–3.07 | <.001 | 2.96 | 1.82–4.81 | <.001 | – | – | – | 1.99 | 1.30–3.05 | .002 |
| >5mitosis rate/mm2 | 3.99 | 1.24–12.94 | .021 | – | – | – | – | – | – | – | – | – |
Variables with statistical significance <0.20 were considered as potential factors for inclusion in the multivariate model (bold).
DMFS, distant metastases-free survival; MSS, melanoma specific survival; OS, overall survival; RFS, recurrence free survival; HR, hazard ratio; CI, confidence interval.
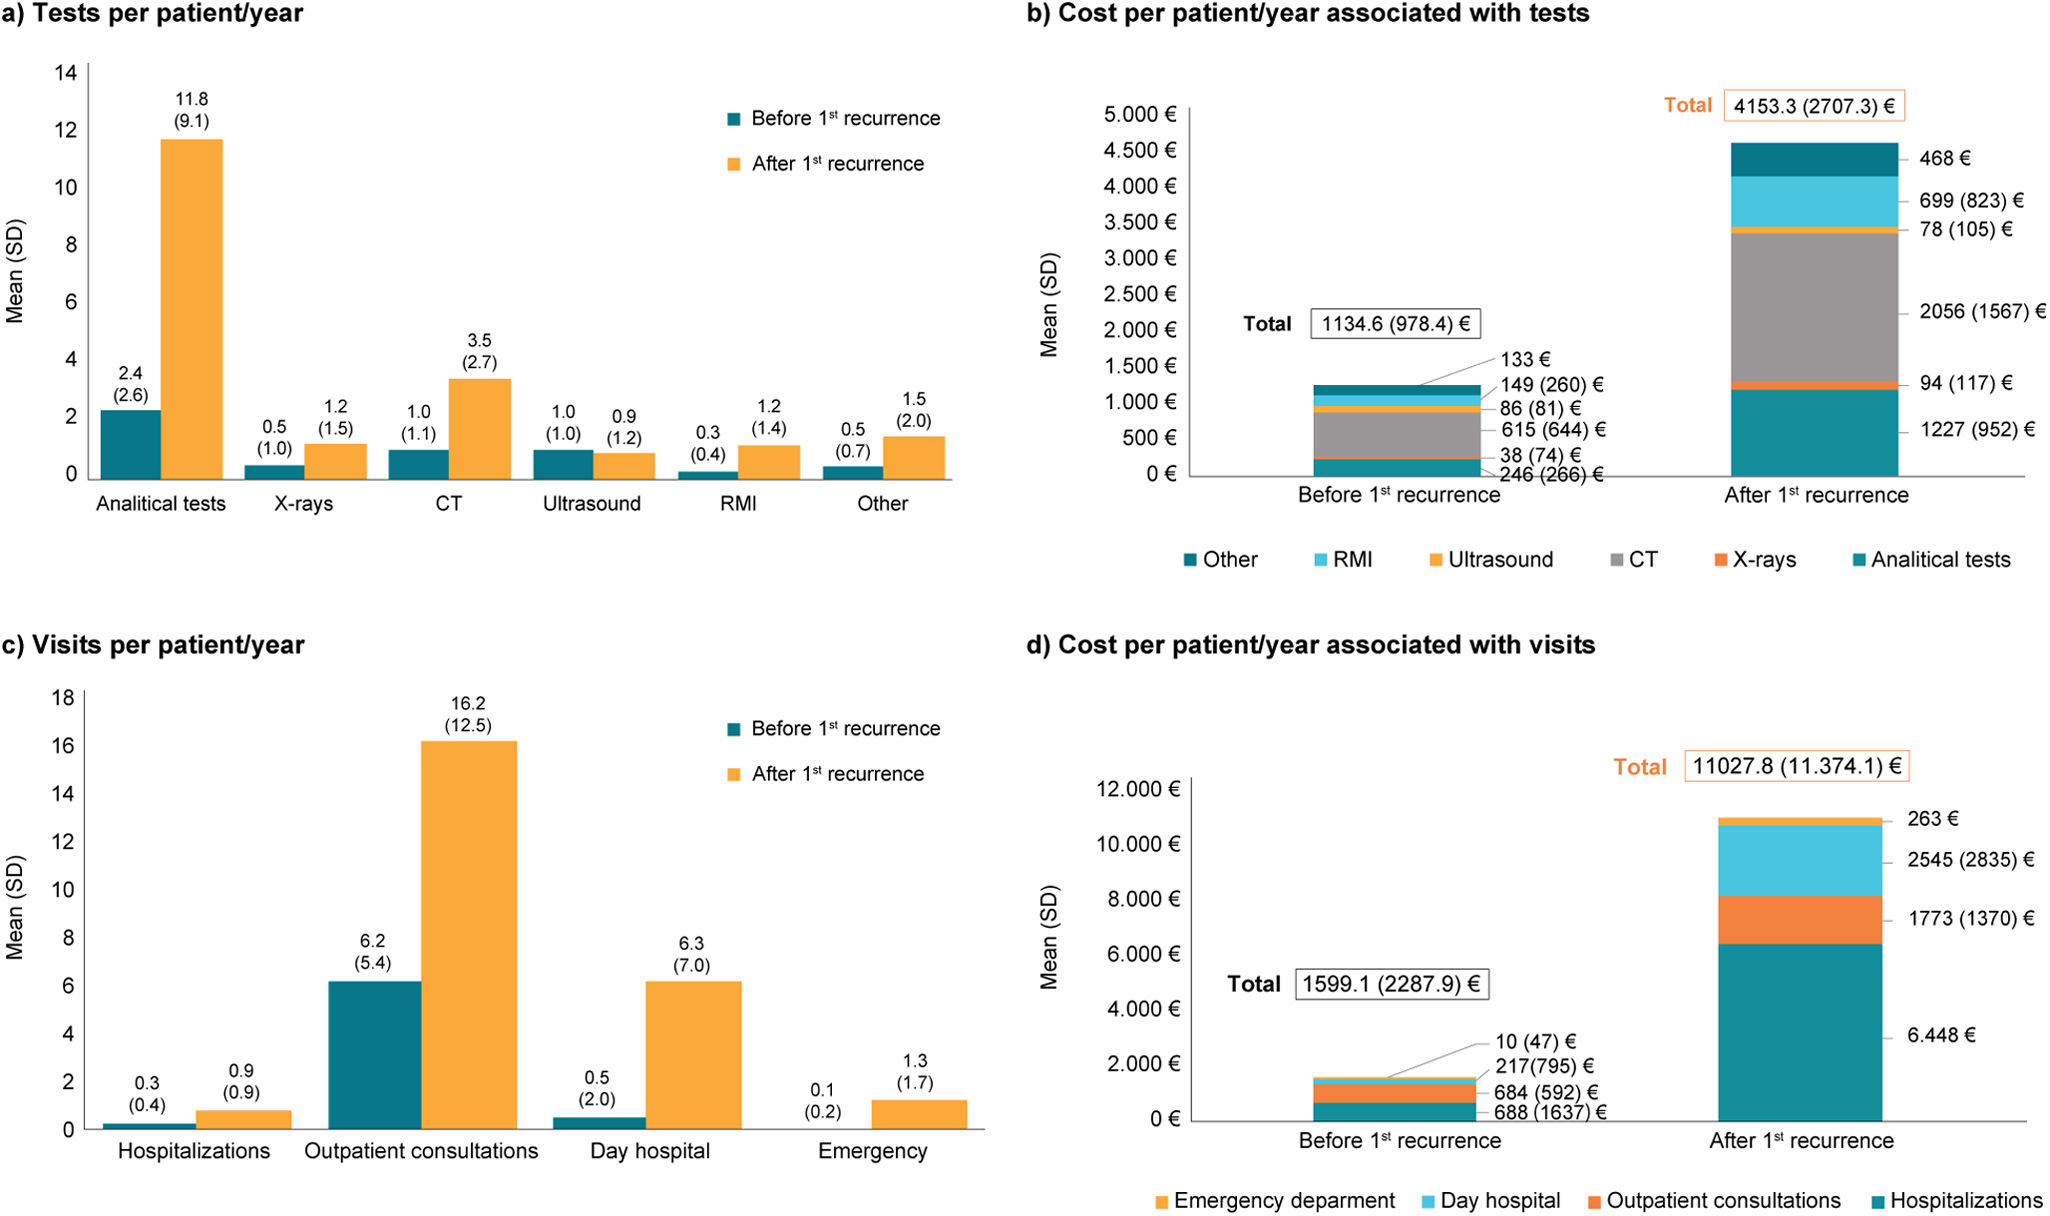
After first recurrence, annual use of all diagnostic tests except ultrasound increased (Fig. 3A), raising annualized cost of diagnostic tests per patient from €1134.61 to €4153.29 (Fig. 3B). Annual number of medical visits also increased (Fig. 3C), with costs rising from €1599.10 to €11,027.83 (Fig. 3D). In addition, annual treatment cost per patient increased by €38,932.54 after first recurrence, mostly because of pharmacologic treatment (Supplementary Fig. 3A).

Overall, total annual cost per patient increased by 91%, from €5254.90 before recurrence to €56,969.80 after recurrence (Supplementary Fig. 3B).
Patients with stage IIB/IIC disease had higher healthcare costs than those with stage IIA both before and after recurrence, mainly because of higher pharmacologic costs (Supplementary Table 1).
DiscussionIn the METHEOR study, we examined recurrence patterns in patients with pathologic stage II primary CM and changes in HCRU at disease progression in real-world clinical practice in Spain. We identified 324 adult patients: 44% had stage IIA, 36% stage IIB, and 20% stage IIC disease. After a median follow-up of more than 5 years, 27.8% had melanoma recurrence, similar to rates reported in other studies of stage II CM (27.2–29.6%).6,11,12
In our study, 54.4% of patients had distant first recurrences, a proportion similar to that reported by Bleicher et al.6 (50.6%). Furthermore, the proportion of patients with distant recurrence was similar across all 3 stages (>50%), and almost half of patients had a 2nd recurrence despite treatment. These findings suggest that new management approaches are needed to reduce recurrence.
Consistent with previous reports, recurrence occurred more often in stage IIB (34%) and stage IIC (32%) than in stage IIA disease (21%). In addition, patients with stage IIB or IIC disease have been shown to have worse outcomes than those with stage IIIA disease,17,18 which has prompted discussion as to whether staging should be revisited.7 However, unlike previous reports,17 we observed that stage IIB CM was associated with a significantly increased recurrence risk.
The absence of significant differences in OS among stage IIA, IIB, and IIC patients in our cohort may appear inconsistent with previously published data. One possible explanation lies in the exclusion criteria used in this study. Specifically, patients with vascular invasion or incomplete excision of the primary tumor were excluded to ensure sample homogeneity and avoid potential misclassification. Vascular invasion may be interpreted as an indicator of micrometastatic spread19 and has been associated with a higher risk of dissemination, as well as being an independent prognostic factor for both progression-free survival and OS.20 However, lymphovascular invasion is not currently used to upstage patients under AJCC criteria, and this exclusion may limit the generalizability of survival estimates. It is reasonable to assume that a proportion of stage IIB/IIC patients in real-world settings may present with lymphovascular invasion, which could influence survival curves and explain the lack of prognostic gradient observed in our results.
Because the effectiveness of adjuvant anti–PD-1 therapy for stage III melanoma has been established,21–23 similar strategies have been investigated in resected high-risk stage IIB/IIC melanoma. In the CheckMate 76K study, adjuvant nivolumab in patients with stage IIB or IIC melanoma resulted in a statistically significant improvement in RFS, with a 58% reduction in risk of recurrence or death compared with placebo,24 leading to regulatory approval. Similarly, in the KEYNOTE-716 study, adjuvant pembrolizumab significantly improved RFS and DMFS versus placebo (HR, 0.64 for both) in patients with stage IIB or IIC melanoma, leading to approval.10
Despite these approvals, stage IIB/IIC melanoma remains a high-risk setting requiring further perioperative investigation. Additional studies are needed to identify which patients benefit most from adjuvant therapy. Advancing personalized care will depend on improved biomarker identification and evaluation of the potential role of neoadjuvant therapy in this group.
Further research is also required to identify recurrence risk factors and predictors beyond staging criteria.25 Consistent with previous population-based findings, we identified older age and mitotic rate greater than 5/mm2 as predictors of recurrence, highlighting the prognostic value of mitotic activity.26,27
As previously reported, recurrence in our cohort was associated with a substantial increase in HCRU and related costs.28 Mean healthcare costs were slightly higher in patients with stage IIB or IIC disease than in those with stage IIA. Given the expected future burden of melanoma in Europe, driven by population aging and increased awareness and early detection, the number of new cases is likely to rise. Allocation of resources for disease control is therefore crucial, particularly as new therapies are rapidly being developed.29 In addition, healthcare resources should be focused on the highest-risk patients, especially those with stage IIB and IIC disease, who are most likely to benefit from adjuvant anti–PD-1 therapy, while treatment may be de-escalated in lower-risk patients to optimize resource use.
This study was limited by its retrospective design. After the inclusion period defined for this study, the EMA approved adjuvant anti-PD-1 therapies (nivolumab or pembrolizumab) for stage II CM, so real-world data on the effect of these therapies on survival outcomes were not available. In addition, some patients did not receive treatment after recurrence, which may have led to underestimation of associated health care resource use.
In conclusion, more than one-quarter of patients with stage II CM developed recurrence. More than half of these patients developed distant metastases, which may have a substantial impact on survival. These results highlight the need for improved follow-up and treatment strategies to reduce recurrence risk in patients with stage II CM, especially in stage IIB/IIC disease. However, patients with stage IIA disease also had a substantial recurrence risk, and clinical trials of adjuvant therapy in this setting are warranted.
FundingThis study was sponsored by Bristol Myers Squibb.
Conflicts of interestE. Nagore participated as principal investigator and coordinator of the METHEOR study funded by BMS; received grants from the Generalitat Valenciana; consulting fees from Almirall; and support for attending meetings and/or travel from Cantabria Labs and ISDIN. He is a member of the Project & Proposals Committee of the EADV and Director of Actas Dermosifiliográficas of the AEDV.
E. Samaniego received payment or honoraria for presentations or educational events from Sun Pharma, Novartis, and BMS, and participated in advisory boards with Sun Pharma.
R. Fernández-de-Misa received payment or honoraria for presentations from Takeda, Kyowa Kirin, Recordati, and BMS.
F. Vílchez-Márquez received payment or honoraria for presentations and participated in advisory boards with Sun Pharma, Pierre Fabre, Almirall, and Kyowa Kirin.
S. Puig received payment or honoraria for presentations from Almirall, Avène, Bioderma, Cantabria Labs, Eucerin, ISDIN, La Roche-Posay, Pierre Fabre, Regeneron, and Sanofi; participated in advisory boards with Almirall, ISDIN, La Roche-Posay, MSD, Novartis, Pfizer, Sanofi, and Sun Pharma; received grants from Almirall, La Roche-Posay, and Cantabria Labs; has other financial interests with Damae Médica; and has nonfinancial interests with La Roche-Posay and Leo Pharma.
L. Ostios-García and D. Vilanova are employees of BMS.
A. Boada, A. Diago, P. Ortiz-Romero, S. Moreno, L. Ferrándiz, and A. Flórez declare no conflicts of interest.
The authors thank all the investigators whose collaboration made the METHEOR study possible.
Medical writing support was provided by María Yuste, Evidenze Health España, funded by Bristol Myers Squibb. Responsibility for opinions, conclusions, and interpretation of the data lies with the authors.
The following are the supplementary data to this article:

Kaplan–Meier curve of recurrence-free survival by stage (IIA, IIB and IIC) (a) and overall survival by stage (IIA, IIB and IIC) (b).

Kaplan–Meier curve of melanoma-specific survival for all patients (a), and by stage IIA versus IIB/C (b) by stage (IIA, IIB and IIC) (c) and distant metastasis-free survival for all patients (d) and by substage IIA versus IIB/C (e) and by stage (IIA, IIB and IIC) (f).

Annual treatment associated and total cost before and after first recurrence.




