




Repair of surgical defects in the plantar area represents a surgical challenge due to restricted movement of the local tissue in this region, poor skin circulation, and the requirement for weight-bearing support in the area.1 Treatment selection takes into consideration the size and depth of the defect, as well as each patient's individual characteristics.2
Currently, there are several alternatives that provide durable, painless, functional, and aesthetically satisfactory coverage in this area. Among the different options are skin grafts, which are preferred for smaller defects (<3cm) or as temporary coverage. Simple and complex flaps are used for larger defects, although they usually involve longer surgical time, greater morbidity for the patient, and more extensive postoperative care.1
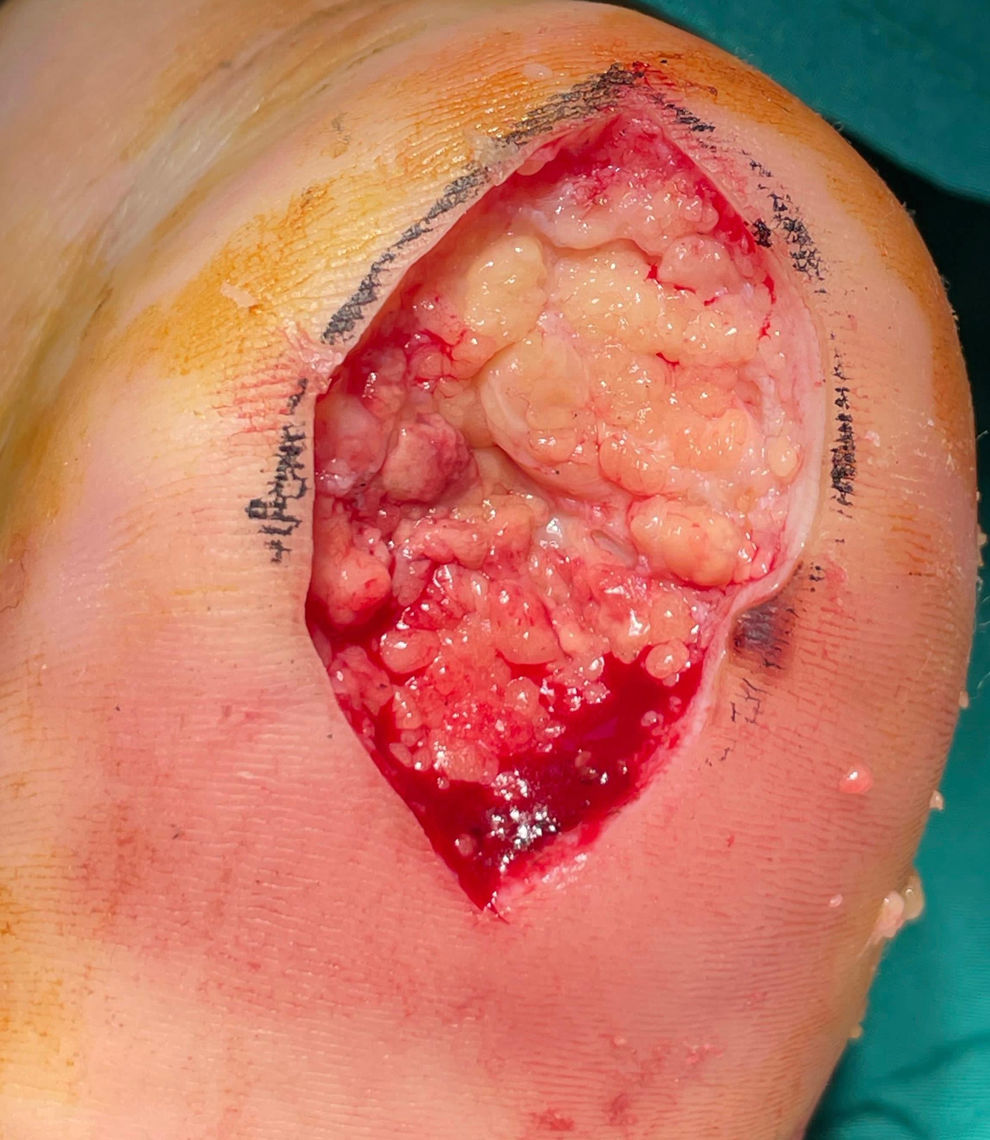
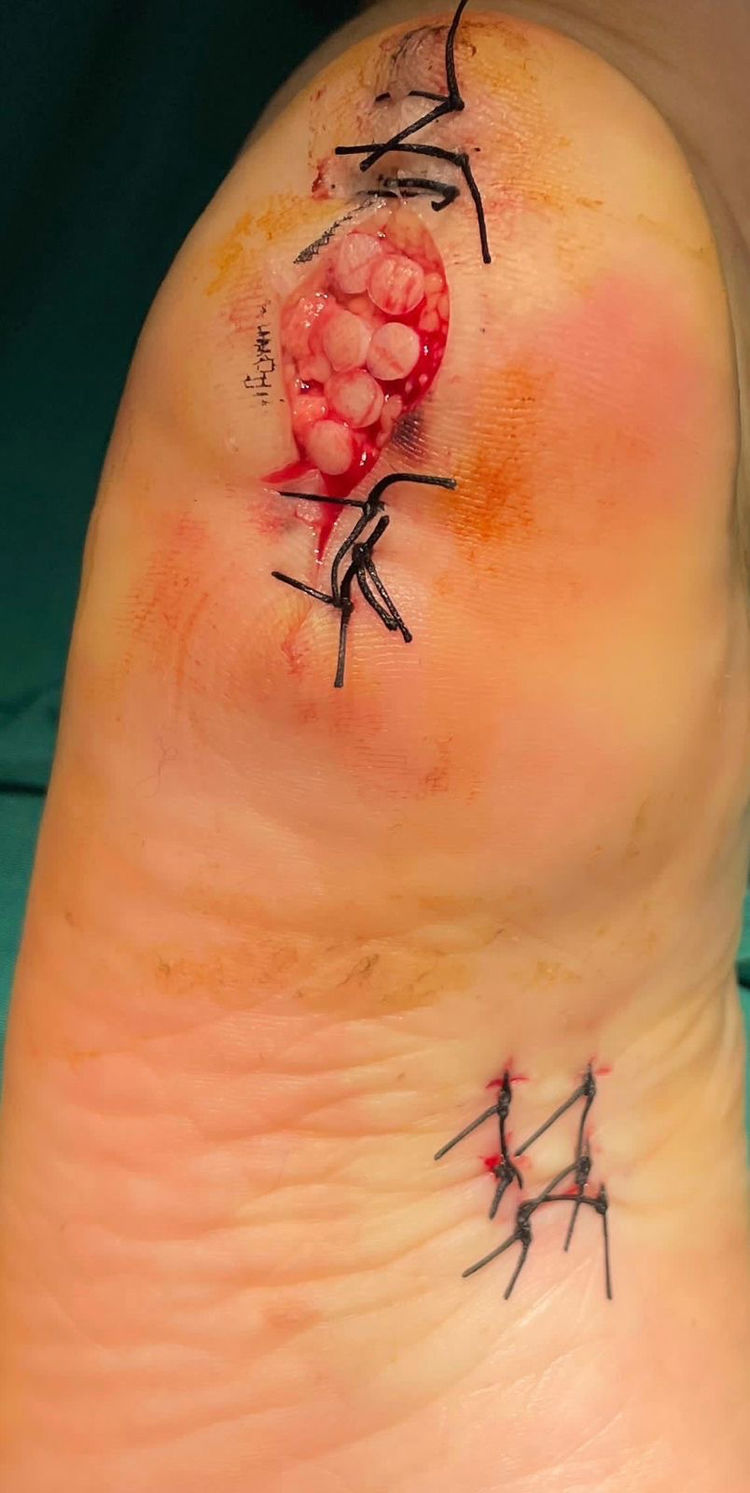
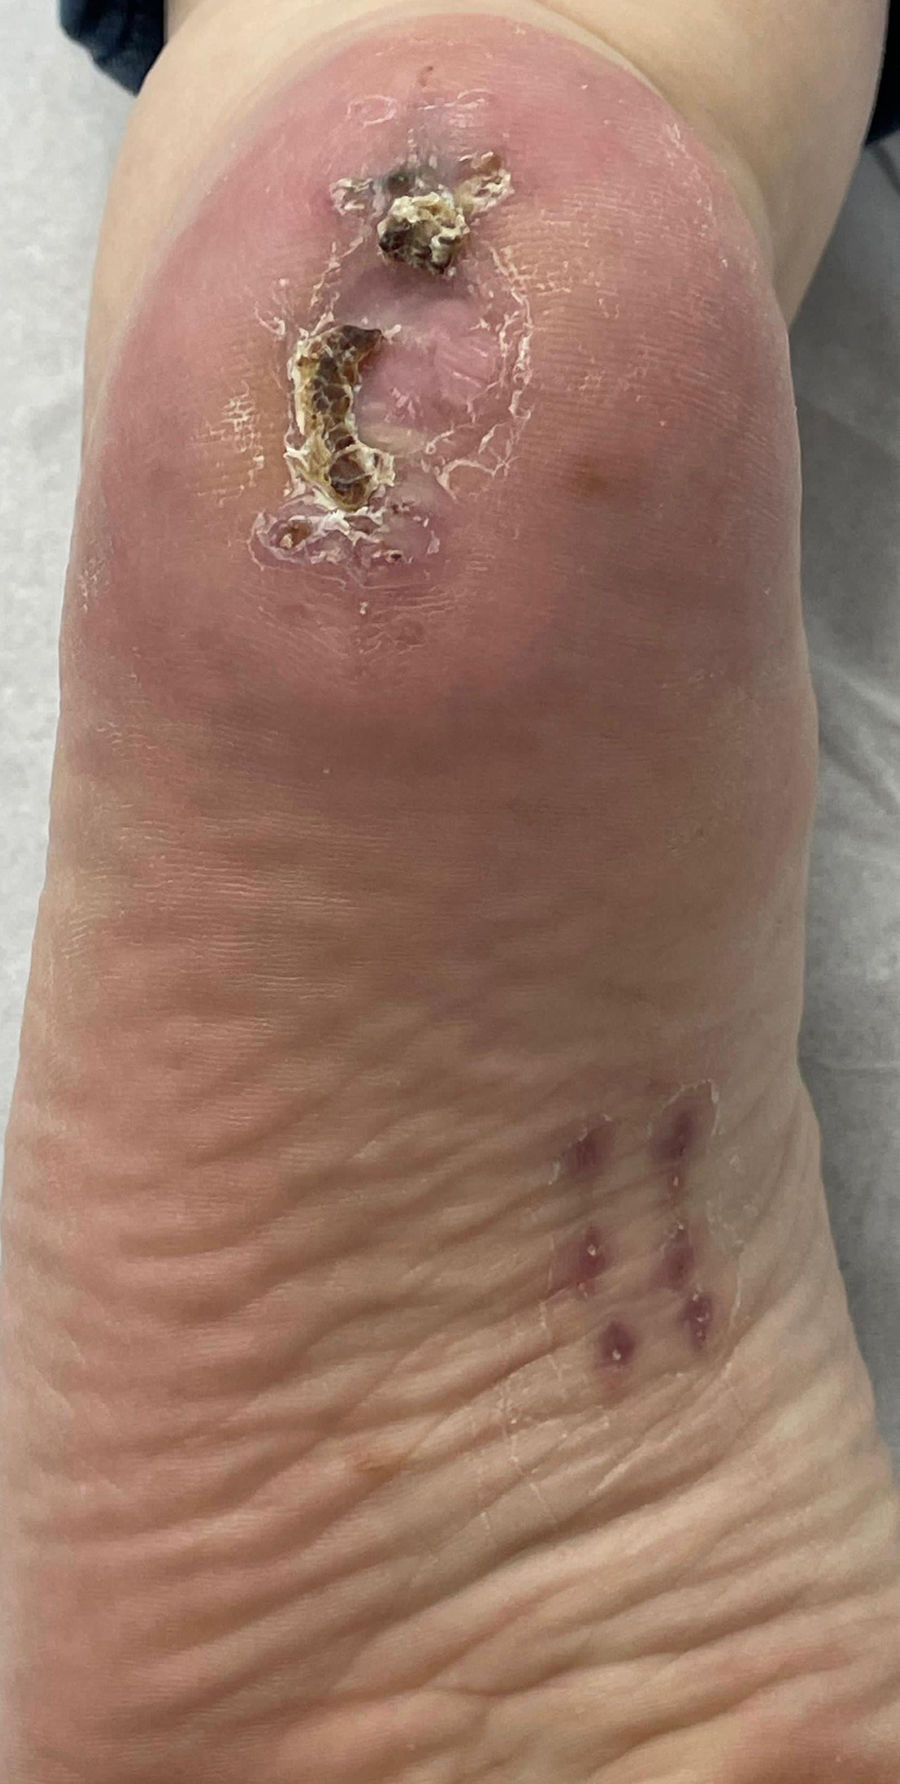
We describe the case of a 61-year-old woman with no relevant past medical history, whose physical examination revealed an irregularly bordered hyperpigmented macule on the left heel. Dermoscopy showed a ridge pattern suggestive of melanoma. There were no palpable lymph nodes. An excisional biopsy of the lesion was performed. Histopathological analysis showed findings consistent with acral melanoma in situ. Definitive treatment was performed with a 5-mm extension from the scar, resulting in a 5×2.5-cm defect on the left heel (Fig. 1). First, primary closure of both edges of the lozenge-shaped defect was performed. Then, 6 full-thickness skin micrografts obtained with a No. 4 punch were applied to the central area of the defect. The donor site was the skin of the plantar arch of the same foot, a location chosen because it is a non-weight-bearing area, and it was closed with simple sutures (Fig. 2). The patient progressed uneventfully during follow-up visits, undergoing weekly dressings with paraffin gauze and a secondary dressing with nonwoven gauze covered externally by a hypoallergenic acrylic adhesive. Complex dressings or negative-pressure therapy were not required. The sutures were removed at 3 weeks, with a good and rapid aesthetic and functional result at 5 weeks (Fig. 3).


Optimal reconstruction of any defect seeks to obtain the best functional and morphological results while maintaining the lowest possible morbidity for the patient. Micrografts or punch grafts are a type of full-thickness skin autograft that, in addition to providing coverage, have an angiogenic effect and release growth factors, promoting contraction and epithelialization of the defect. They have therefore been associated with anti-inflammatory and analgesic capacity and with a shorter healing time.3
Therefore, this technique allows the defect to be repaired with advantages for both the treating team and the patient. On the one hand, it is a simpler surgical technique, with shorter surgical time and performed under local anesthesia. On the other hand, it avoids adding morbidity, provides a better cosmetic outcome at the donor site, and reduces the patient's recovery time, with excellent functional and aesthetic results.
We present this reconstructive option for acral skin defects of the foot, using a simple technique that provides an effective and rapid result for the patient.
FundingNone declared.
Conflicts of interestsNone declared.




