





Atopic dermatitis (AD) is a common chronic inflammatory disease that presents differences in clinical expression according to sex. The aim of this study was to evaluate the influence of sex on disease severity, comorbidities, treatments, and adverse events in patients with moderate-to-severe AD included in the Spanish BIOBADATOP registry.
MethodsWe conducted a prospective observational study using data from the BIOBADATOP registry from March 2020 to February 2025. Demographic variables, severity scales (EASI, DLQI, POEM, pruritus VAS), comorbidities, treatments, and adverse events were collected. Statistical analysis was performed using Chi-square, Student's t-test, and Mann–Whitney tests, considering statistical significance at P<.05.
ResultsA total of 507 adult patients on systemic treatment were included (53.1% men, 46.9% women). Men showed greater disease severity according to EASI (21.7 vs 21.0) and higher serum IgE levels (1323 vs 638KU/L). Women reported greater pruritus intensity and worse POEM scores. Anxiety (26% vs 13%) and depression (15% vs 5%) were more frequent among women. No differences were observed in family history or atopic comorbidities. Similarly, no relevant differences were found in treatments received, treatment duration, or clinical response at 3, 6, and 12 months. However, women showed a higher rate of GI adverse events (97/1000 vs 19/1000 patient-years).
ConclusionsClinical and comorbidity differences according to sex exist in moderate-to-severe AD. Men show greater disease severity and higher IgE levels, whereas women experience a greater perceived disease burden, pruritus, psychiatric comorbidities, and more GI adverse events. These findings support the need to consider sex as a factor in the evaluation and comprehensive management of AD.
La dermatitis atópica (DA) es una enfermedad inflamatoria crónica frecuente que presenta diferencias de expresión clínica según el sexo. El objetivo del estudio fue evaluar la influencia del sexo en la gravedad, comorbilidades, tratamientos y eventos adversos en pacientes con DA moderada-grave incluidos en el registro español BIOBADATOP.
MétodoSe realizó un estudio observacional prospectivo con datos del registro BIOBADATOP desde marzo de 2020 hasta febrero de 2025. Se recogieron variables demográficas, escalas de gravedad (EASI, DLQI, POEM, EVA prurito), comorbilidades, tratamientos y eventos adversos. El análisis estadístico se efectuó con pruebas de chi cuadrado, t de Student y Mann-Whitney, considerando significación en p<0,05.
ResultadosSe incluyeron 507 pacientes adultos (53,1% hombres, 46,9% mujeres) en tratamiento sistémico. Los hombres presentaron mayor gravedad en EASI (21,7 vs 21,0) y niveles séricos de IgE (1323 vs 638 KU/L). Las mujeres refirieron mayor prurito y peor puntuación en POEM. La ansiedad (26% vs 13%) y depresión (15% vs 5%) fueron más frecuentes en mujeres. No se observaron diferencias en antecedentes familiares ni en comorbilidades atópicas. Tampoco hubo diferencias relevantes en tratamientos recibidos, duración, ni respuesta clínica a los 3, 6 y 12 meses. Sin embargo, las mujeres presentaron mayor tasa de efectos adversos gastrointestinales (97/1000 vs 19/1000 pacientes-año).
ConclusionesExisten diferencias clínicas y de comorbilidad según el sexo en la DA moderada-grave. Los hombres muestran mayor gravedad y niveles de IgE más altos, mientras que las mujeres experimentan un mayor impacto percibido de la enfermedad, prurito y comorbilidades psiquiátricas, además de más efectos adversos digestivos. Estos hallazgos apoyan la necesidad de considerar el sexo como un factor en la evaluación y manejo integral de la DA.
Atopic dermatitis (AD) is a chronic inflammatory skin disease characterized by eczematous lesions with a relapsing course that affects millions of people worldwide. The estimated prevalence of AD varies according to age and, based on studies conducted in developed countries, is approximately 15% in the pediatric population1 and around 7% in the adult population.2
Whereas during childhood the disease affects both sexes equally, AD and other atopic disorders have been observed to show a female predominance, especially during adolescence and adulthood.2–5 In addition, women may present a different risk of developing associated comorbidities, such as asthma, allergic rhinitis, and psychiatric disorders including anxiety and depression.5–7 Differences between sexes have also been observed regarding administered treatments and treatment adherence, as well as in the frequency of adverse events, highlighting the importance of considering sex as a key factor in the management of AD.8,9
There are few studies evaluating sex differences in patients with AD, and given the growing evidence that sex plays an important role in AD, the aim of this study was to evaluate and describe the influence of sex on disease severity, the presence of comorbidities, treatments used, and the occurrence of adverse events, in order to obtain an overall view of sex differences in patients with AD receiving systemic therapy in Spain.
Materials and methodsFor this study, patients from the Spanish Atopic Dermatitis Registry (BIOBADATOP) were used, which has been previously described.10 This study is a prospective, multicenter observational cohort that, since its initiation in March 2020, has included pediatric, adolescent, and adult patients with AD, mainly with moderate-to-severe disease, who initiated systemic immunomodulatory treatment. At baseline visits, demographic data, diagnosis-related information, and baseline severity data measured using the Eczema Area and Severity Index (EASI), Dermatology Life Quality Index (DLQI), Patient-Oriented Eczema Measure (POEM), and pruritus during the previous week assessed using a visual analog scale (VAS) were collected. Similarly, information regarding comorbidities and previous treatments used was also recorded. During follow-up visits, changes in AD severity and changes to systemic treatments, along with the reasons for treatment discontinuation, were documented. In addition, adverse events (AEs) occurring during follow-up were collected using the MedDRA dictionary.
We carried out patient data collection in the registry through assignment of a unique pseudonymized identification code using the online data capture system Research Electronic Data Capture (REDCap).
We conducted a descriptive analysis of adult patients included from study initiation (March 2020) to the latest available cutoff date (February 2025) according to sex, defined as biological sex at birth.
Statistical analysis was performed using Stata software (version 17.0, Statacorp, Texas, United States). Data were described using conventional statistics (means and standard deviations, medians and quartiles, or absolute and relative frequencies). Subsequently, differences between groups were compared using the Chi-square test, Student's t test, or the Mann–Whitney U test, as appropriate. Visual presentations using boxplots of the different parameters throughout follow-up according to sex were also performed. P values<.05 were considered statistically significant.
The BIOBADATOP registry received approval from the Aragón Clinical Research Ethics Committee (PA18/051). All patients gave their written informed consent prior to inclusion in the study.
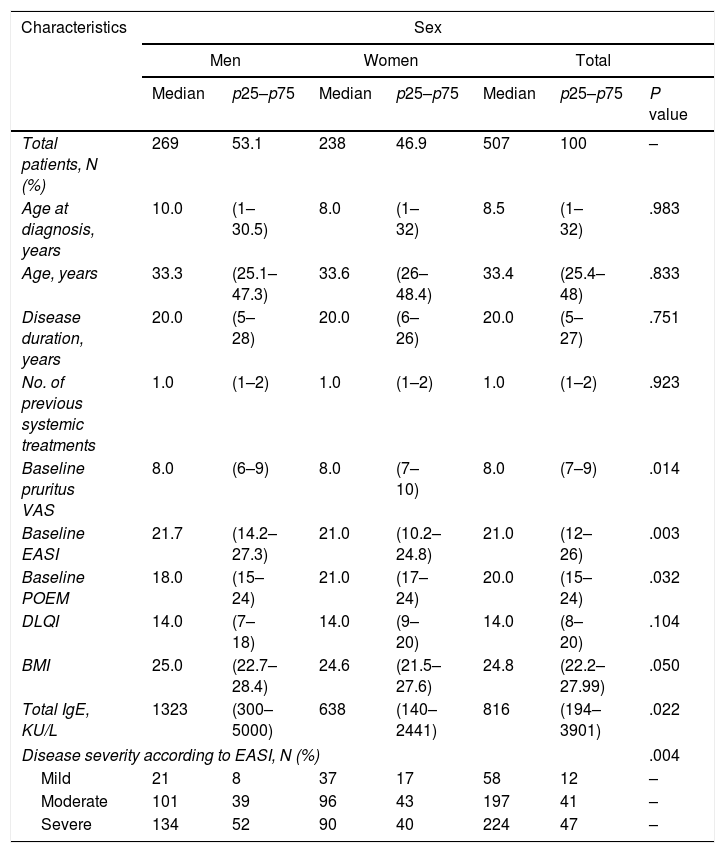
ResultsPopulation characteristics according to sexA total of 507 adult patients with AD on systemic therapies from the BIOBADATOP registry were included, 53.1% (N=269) men and 46.9% (N=238) women, with a median age of 33.4 years and an IQR of 25.4–48.0 years. Regarding baseline scales, there were slight statistically significant differences between men and women in median EASI (P=.003), which was slightly more severe in men (EASI 21.7 vs 21.0 in women), pruritus VAS (P=.014), with higher scores in women, POEM (P=.032), with greater impairment in women (POEM 21 vs 18 in men), and serum IgE levels (P=.022), which were higher in men, with a median of 1323KU/L vs 638KU/L in women. No differences were found for DLQI.
The clinical characteristics of the patients included in the study are shown in Table 1.
Characteristics of the population according to sex.
| Characteristics | Sex | ||||||
|---|---|---|---|---|---|---|---|
| Men | Women | Total | |||||
| Median | p25–p75 | Median | p25–p75 | Median | p25–p75 | P value | |
| Total patients, N (%) | 269 | 53.1 | 238 | 46.9 | 507 | 100 | – |
| Age at diagnosis, years | 10.0 | (1–30.5) | 8.0 | (1–32) | 8.5 | (1–32) | .983 |
| Age, years | 33.3 | (25.1–47.3) | 33.6 | (26–48.4) | 33.4 | (25.4–48) | .833 |
| Disease duration, years | 20.0 | (5–28) | 20.0 | (6–26) | 20.0 | (5–27) | .751 |
| No. of previous systemic treatments | 1.0 | (1–2) | 1.0 | (1–2) | 1.0 | (1–2) | .923 |
| Baseline pruritus VAS | 8.0 | (6–9) | 8.0 | (7–10) | 8.0 | (7–9) | .014 |
| Baseline EASI | 21.7 | (14.2–27.3) | 21.0 | (10.2–24.8) | 21.0 | (12–26) | .003 |
| Baseline POEM | 18.0 | (15–24) | 21.0 | (17–24) | 20.0 | (15–24) | .032 |
| DLQI | 14.0 | (7–18) | 14.0 | (9–20) | 14.0 | (8–20) | .104 |
| BMI | 25.0 | (22.7–28.4) | 24.6 | (21.5–27.6) | 24.8 | (22.2–27.99) | .050 |
| Total IgE, KU/L | 1323 | (300–5000) | 638 | (140–2441) | 816 | (194–3901) | .022 |
| Disease severity according to EASI, N (%) | .004 | ||||||
| Mild | 21 | 8 | 37 | 17 | 58 | 12 | – |
| Moderate | 101 | 39 | 96 | 43 | 197 | 41 | – |
| Severe | 134 | 52 | 90 | 40 | 224 | 47 | – |
DLQI: Dermatology Life Quality Index; EASI: Eczema Area and Severity Index; VAS: Visual Analog Scale; POEM: Patient-Oriented Eczema Measure; p25: 1st quartile; p75: 3rd quartile.
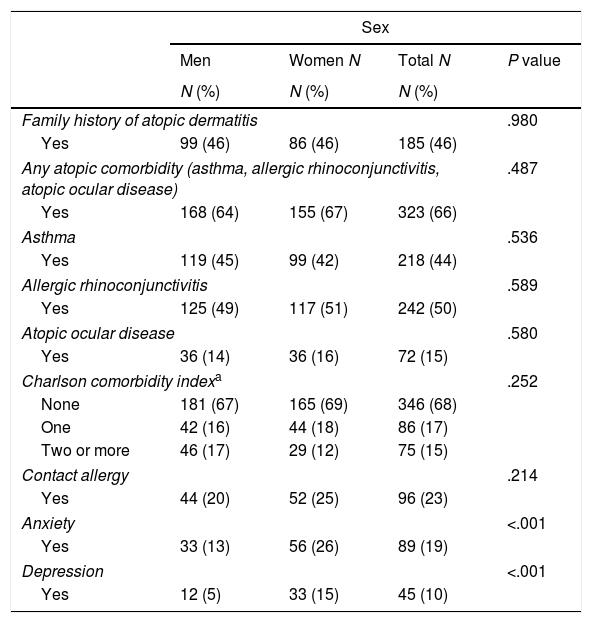
Statistically significant differences were found in psychiatric-related comorbidities, with women showing higher percentages vs men for anxiety (26% vs 13% in men; P<.001) and depression (15% vs 5% in men; P<.001). However, no differences were found regarding family history or atopic comorbidities. Allergic rhinoconjunctivitis was the most frequent comorbidity, affecting 55% of the total population, followed by asthma (44%), atopic ocular disease (15%), and the Charlson comorbidity index (Table 2).
Prevalence of comorbidities according to sex.
| Sex | ||||
|---|---|---|---|---|
| Men | Women N | Total N | P value | |
| N (%) | N (%) | N (%) | ||
| Family history of atopic dermatitis | .980 | |||
| Yes | 99 (46) | 86 (46) | 185 (46) | |
| Any atopic comorbidity (asthma, allergic rhinoconjunctivitis, atopic ocular disease) | .487 | |||
| Yes | 168 (64) | 155 (67) | 323 (66) | |
| Asthma | .536 | |||
| Yes | 119 (45) | 99 (42) | 218 (44) | |
| Allergic rhinoconjunctivitis | .589 | |||
| Yes | 125 (49) | 117 (51) | 242 (50) | |
| Atopic ocular disease | .580 | |||
| Yes | 36 (14) | 36 (16) | 72 (15) | |
| Charlson comorbidity indexa | .252 | |||
| None | 181 (67) | 165 (69) | 346 (68) | |
| One | 42 (16) | 44 (18) | 86 (17) | |
| Two or more | 46 (17) | 29 (12) | 75 (15) | |
| Contact allergy | .214 | |||
| Yes | 44 (20) | 52 (25) | 96 (23) | |
| Anxiety | <.001 | |||
| Yes | 33 (13) | 56 (26) | 89 (19) | |
| Depression | <.001 | |||
| Yes | 12 (5) | 33 (15) | 45 (10) | |
Charlson comorbidities: myocardial infarction, heart failure, peripheral arterial disease, cerebrovascular disease, dementia, chronic respiratory disease, connective tissue disease, peptic ulcer disease, mild chronic liver disease, moderate/severe chronic liver disease, diabetes, diabetes with target organ damage, hemiplegia, moderate/severe chronic kidney disease, solid tumor or malignancy, metastatic solid tumor, leukemia, lymphoma, and defined AIDS.
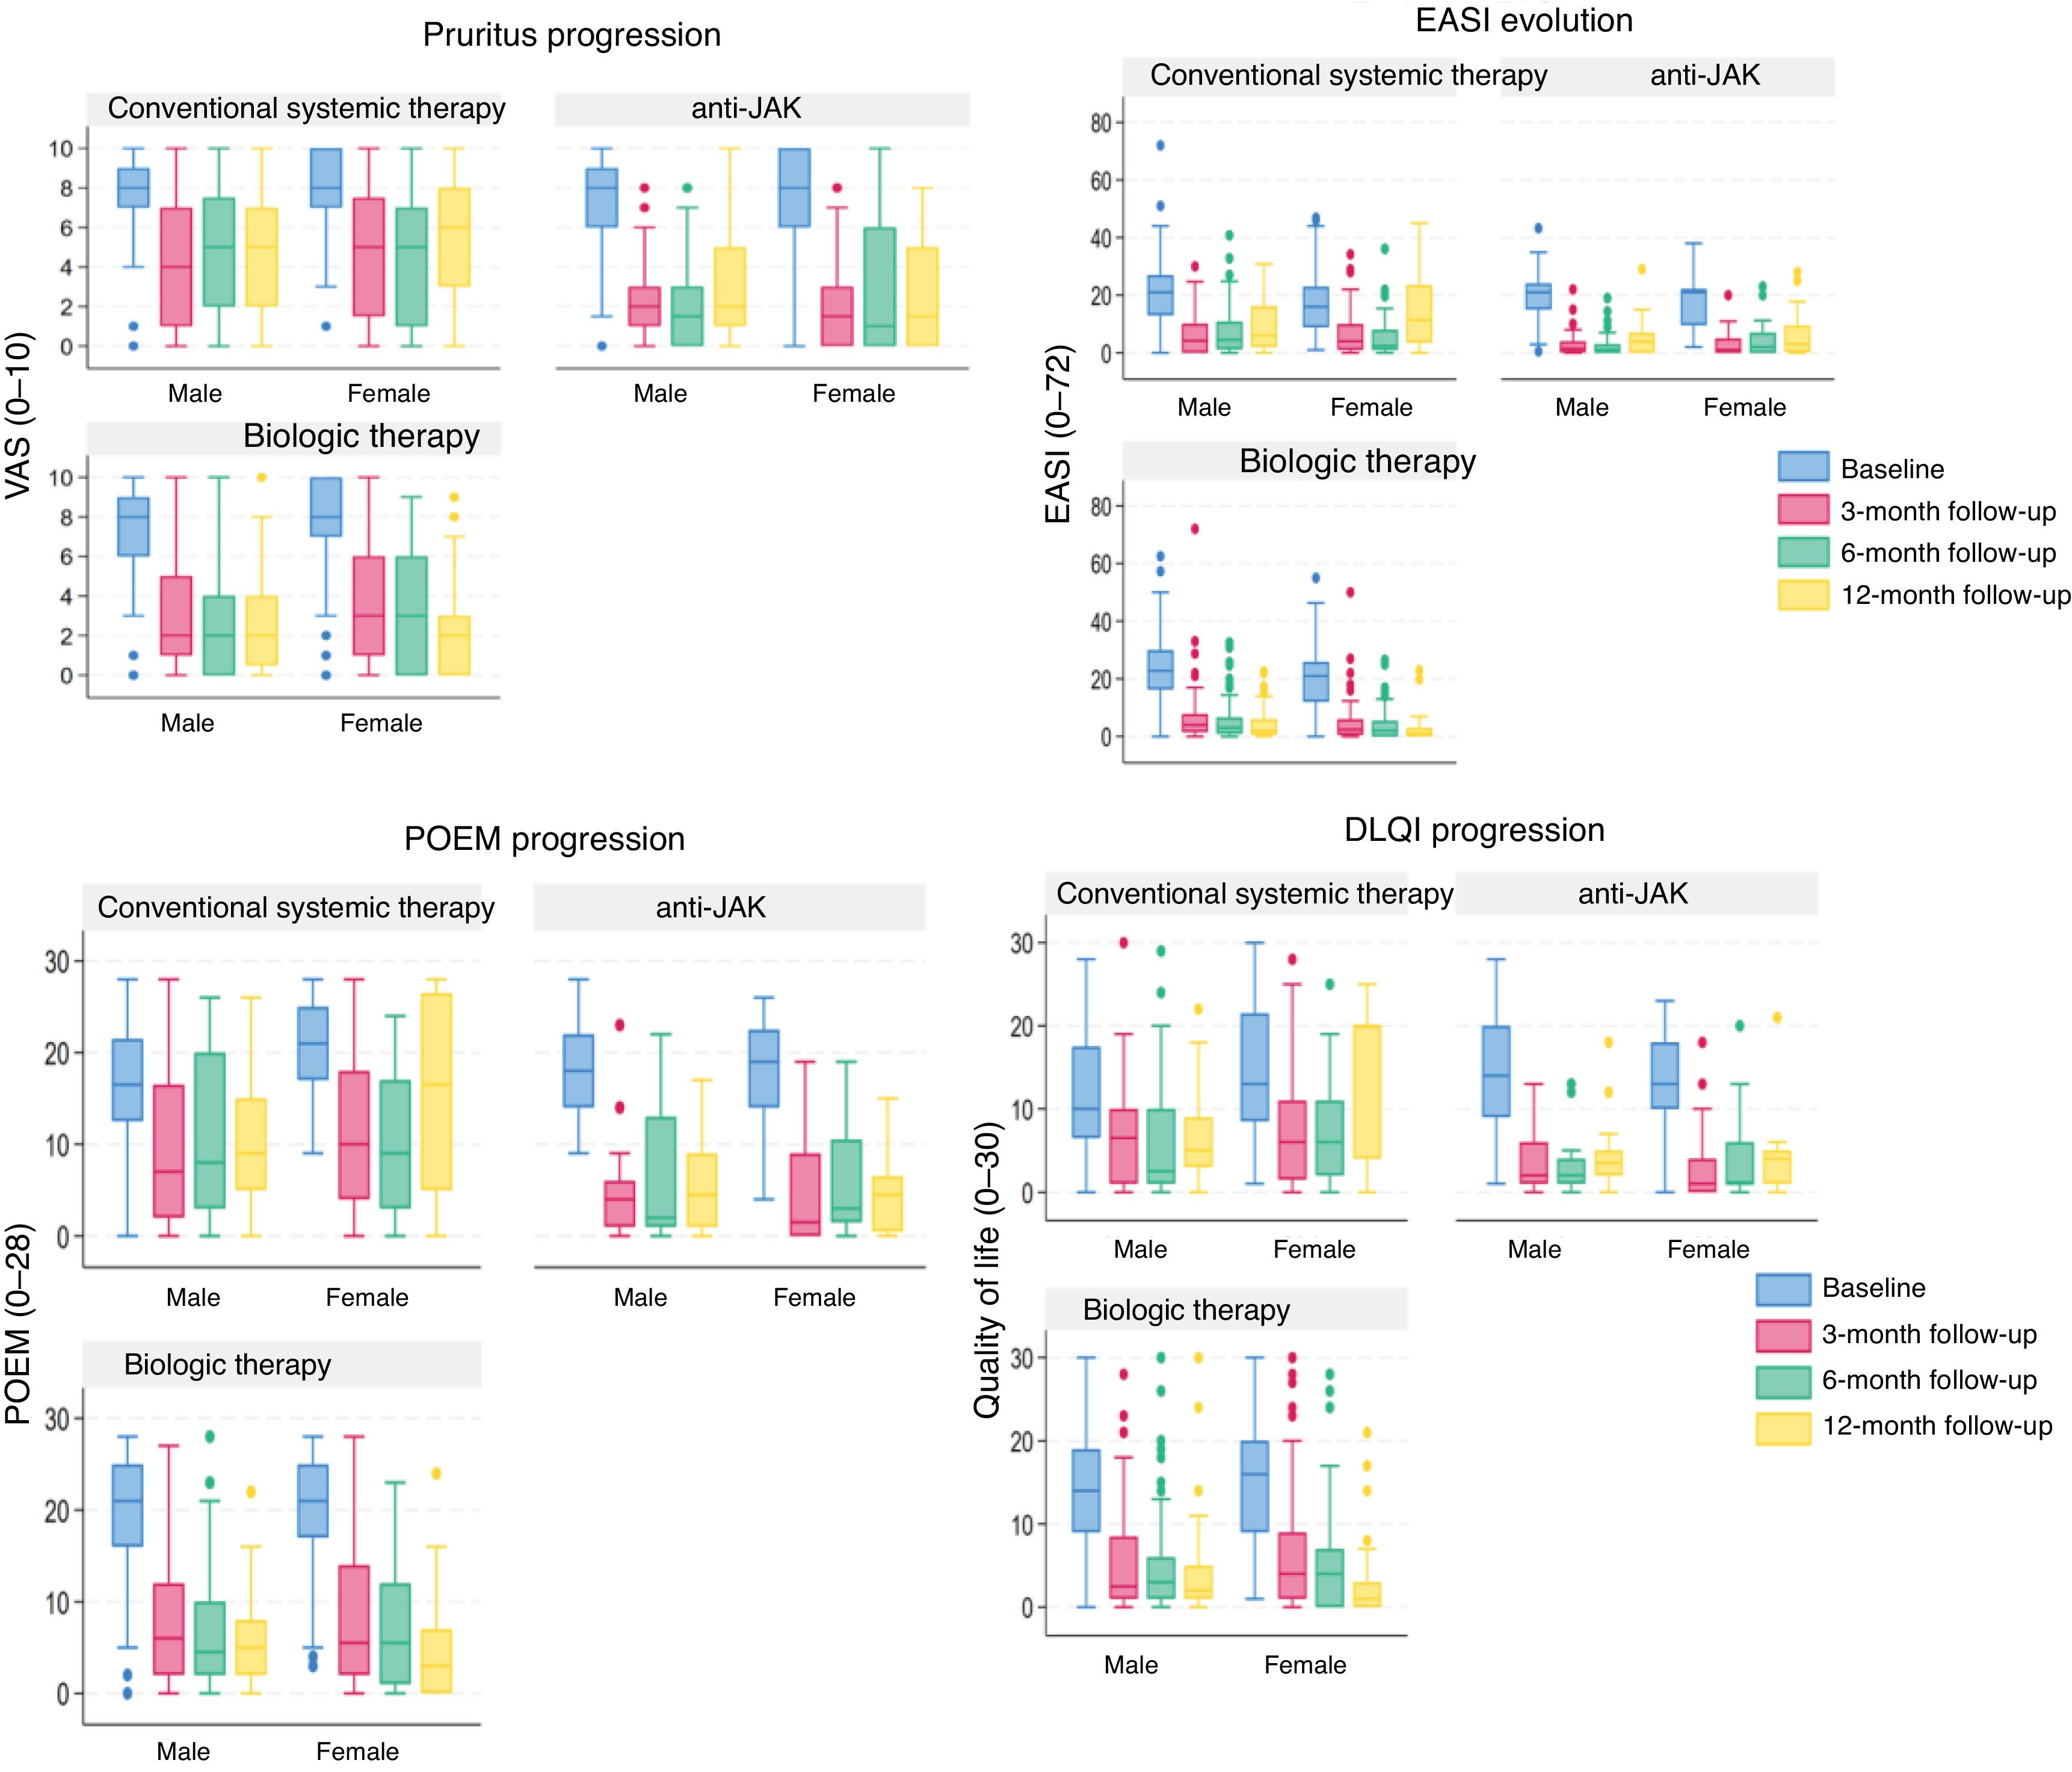
No differences were observed between both groups for the treatment-related variables evaluated, neither regarding the treatment received (conventional systemic therapy, anti-JAK therapy, or biologic therapy), nor regarding drug exposure time. Additionally, no differences were found in response to systemic treatments at 3, 6, and 12 months (Fig. 1), nor in the reasons for treatment discontinuation (Table 3).

Box plots of the response to systemic treatments at 3, 6, and 12 months according to sex. Responses were evaluated using severity measurement scales for atopic dermatitis, including EASI, the quality-of-life scales DLQI and POEM, and Pruritus VAS. No significant differences were observed between patients according to sex.
Treatments received according to sex (first treatment).
| Men | Women | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| Systemic treatment | |||||||||
| Classic systemic | Anti-JAK | Biologic | Classic systemic | Anti-JAK | Biologic | P value Classic systemic | P value anti-JAK | P value Biologic | |
| N (%) | N (%) | N (%) | N (%) | N (%) | N (%) | ||||
| Total patients | |||||||||
| Initial N | 86 | 45 | 138 | 84 | 35 | 119 | – | – | – |
| N at 3 months | 54 | 36 | 106 | 57 | 25 | 96 | – | – | – |
| N at 6 months | 63 | 36 | 124 | 60 | 27 | 102 | – | – | – |
| N at 12 months | 31 | 25 | 86 | 28 | 17 | 74 | – | – | – |
| Total person-years of exposure (drug) | 60 | 48 | 204 | 66 | 29 | 163 | – | – | – |
| Drug duration, years, median (p25–p75) | 0.5 (0.3–1.0) | 0.9 (0.5–1.3) | 1.0 (0.6–2.1) | 0.5 (0.3–1.0) | 0.6 (0.3–1.1) | 1.0 (0.5–1.9) | – | – | – |
| Mean reduction in pruritus VAS, mean (SD) | |||||||||
| 3 months | 4.2 (3.6) | 4.8 (3.3) | 3.9 (3.2) | 3.6 (3.3) | 4.8 (3.7) | 4.0 (3.4) | .405 | .924 | .784 |
| 6 months | 3.0 (3.8) | 5.5 (3.0) | 4.2 (3.2) | 3.7 (4.1) | 4.4 (4.7) | 4.0 (3.7) | .461 | .545 | .728 |
| 12 months | 3.1 (3.8) | 4.2 (4.1) | 4.5 (3.4) | 2.9 (3.8) | 4.9 (3.2) | 5.0 (3.4) | .589 | .725 | .352 |
| Mean reduction in EASI, mean (SD) | |||||||||
| 3 months | 15.2 (13.6) | 16.0 (10.8) | 17.4 (13.0) | 11.7 (12.3) | 13.3 (11.8) | 15.7 (11.9) | .152 | .435 | .449 |
| 6 months | 12.9 (13.0) | 16.3 (8.9) | 18.5 (12.8) | 9.4 (9.7) | 15.8 (11.5) | 16.5 (11.4) | .077 | .901 | .066 |
| 12 months | 9.5 (15.7) | 15.4 (8.4) | 20.3 (14.3) | 4.2 (13.3) | 11.2 (8.8) | 19.3 (12.0) | .096 | .120 | .287 |
| Mean reduction in POEM, mean (SD) | |||||||||
| 3 months | 10.6 (8.4) | 11.6 (8.6) | 12.0 (8.5) | 8.7 (9.6) | 13.1 (10.5) | 11.8 (8.1) | .343 | .520 | .969 |
| 6 months | 7.8 (9.1) | 10.6 (8.5) | 13.1 (8.4) | 10.6 (8.9) | 12.3 (8.6) | 13.4 (8.6) | .241 | .638 | .825 |
| 12 months | 8.1 (7.2) | 12.0 (7.0) | 15.0 (8.4) | 2.9 (9.1) | 13.3 (4.8) | 14.7 (8.1) | .103 | .541 | .880 |
| Mean reduction in DLQI, mean (SD) | |||||||||
| 3 months | 7.6 (10.5) | 8.9 (7.9) | 9.0 (7.1) | 7.3 (9.2) | 7.9 (7.3) | 10.0 (10.3) | .692 | .516 | .279 |
| 6 months | 6.4 (8.1) | 9.6 (7.7) | 10.5 (8.3) | 7.3 (8.4) | 8.5 (9.7) | 10.0 (9.0) | .631 | .698 | .861 |
| 12 months | 8.6 (7.3) | 8.9 (8.0) | 13.2 (8.0) | 7.6 (13.5) | 10.2 (6.7) | 13.2 (8.2) | .582 | .660 | .906 |
| Reason for discontinuation | .614 | .940 | .478 | ||||||
| Lack of efficacy | 32 (45) | 8 (67) | 13 (42) | 30 (44) | 7 (58) | 15 (45) | – | – | – |
| Adverse event | 12 (17) | 1 (8) | 3 (10) | 18 (26) | 2 (17) | 6 (18) | – | – | – |
| Disease remission | 2 (3) | 0 (0) | 2 (6) | 2 (3) | 0 (0) | 0 (0) | – | – | – |
| Other | 19 (27) | 1 (8) | 6 (19) | 15 (22) | 1 (8) | 7 (21) | – | – | – |
Regarding adverse events according to sex, shown in Table 4, statistically significant differences were found in the rate of GI disorders, which was higher in women (97/1000 vs 19/1000 in men; P<.001). No differences were found for the remaining adverse events or adverse outcomes.
Rates of adverse events according to sex.
| Events | P-Y | Rate ×1000 (95%CI) | P value | |
|---|---|---|---|---|
| All adverse events | .430 | |||
| Men | 180 | 312 | 576 (498–667) | |
| Women | 162 | 258 | 628 (538–732) | |
| Serious adverse events | .174 | |||
| Men | 6 | 312 | 19 (9–43) | |
| Women | 10 | 258 | 39 (21–72) | |
| Infections and infestations | .464 | |||
| Men | 55 | 312 | 176 (135–229) | |
| Women | 39 | 258 | 151 (110–207) | |
| Skin and subcutaneous tissue disorders | .330 | |||
| Men | 26 | 312 | 83 (57–122) | |
| Women | 28 | 258 | 108 (75–157) | |
| Eye disorders | .697 | |||
| Men | 22 | 312 | 70 (46–107) | |
| Women | 16 | 258 | 62 (38–101) | |
| GI disorders | <.001 | |||
| Men | 6 | 312 | 19 (9–43) | |
| Women | 25 | 258 | 97 (65–143) | |
| Nervous system disorders | .393 | |||
| Men | 17 | 312 | 54 (34–88) | |
| Women | 10 | 258 | 39 (21–72) | |
| General disorders and administration site conditions | .405 | |||
| Men | 14 | 312 | 45 (27–76) | |
| Women | 8 | 258 | 31 (15–62) | |
| Vascular disorders | .069 | |||
| Men | 5 | 312 | 16 (7–38) | |
| Women | 11 | 258 | 43 (24–77) | |
| Other | .578 | |||
| Men | 35 | 312 | 112 (80–156) | |
| Women | 25 | 258 | 97 (65–143) | |
P-Y: patient-years; 95%CI: 95% confidence interval.
In this study, sex distribution was similar (53.1% men and 46.9% women), with men presenting higher EASI scores and serum IgE levels, whereas women showed greater impairment in POEM scores and higher pruritus intensity according to the VAS scale. Furthermore, psychiatric comorbidities were more frequent in women, with a higher prevalence of anxiety (26% vs 13%) and depression (15% vs 5%). However, no differences were found between sexes regarding the type of systemic treatment received, treatment duration, or clinical response at 3, 6, and 12 months. Finally, a higher rate of gastrointestinal adverse events was reported in women, representing the only significant difference in terms of treatment safety.
Unlike studies conducted in other developed countries, such as that by Chiesa et al.2 carried out in the United States, where 62.4% of patients with AD were women and female sex was associated with a 70% increased likelihood of developing AD vs men, or the study by Pesce et al.4 in Italy, where the prevalence of eczema and AD was higher among older women vs men, no sex-related differences in the prevalence of AD were observed in the present study, although only patients with moderate-to-severe disease requiring systemic treatment were included.
Regarding disease severity and quality-of-life scales, men had higher EASI values, as reported in the study by Salava et al.,11 whereas women obtained higher POEM scores and depression and anxiety were more frequent as comorbidities, which is consistent with findings from former studies. Vinnik et al.7 observed that depression scale scores in women with AD were significantly higher than those in men (46% increase; F(3, 192)=28.17; P<.001), suggesting that this could be explained by higher cortisol levels in women with depression, proposing that differences in cortisol levels according to sex and AD subtype could be related to variations in immune regulation in the context of the disease. Furthermore, Silverberg et al.,12 in a cross-sectional study involving 2893 adults in the United States, demonstrated higher levels and prevalence of anxiety and depression in patients with AD, which increased according to disease severity measured by POEM. These findings reinforce the importance of considering psychological management as an essential component of comprehensive treatment, especially in women, who may require greater emotional and psychological support.
On the other hand, IgE levels were higher in men. Elevated serum IgE levels have been associated with higher EASI scores, although patients with severe AD may occasionally present normal IgE levels.11 Although AD is an immune-mediated disease, it is known that certain changes to the metabolism and balance of sex hormones may play a predisposing role. Testosterone may influence the balance between type 1 and type 2 helper T lymphocytes, IgE synthesis, and eosinophil proliferation. Plasma levels of dehydroepiandrosterone (DHEA) are decreased in patients with AD, and animal models have shown that DHEA administration significantly suppresses the spontaneous increase in both serum IgE and interleukin-6 levels, since DHEA promotes a shift in the Th1/Th2 balance toward Th1-predominant immunity.13,14
Finally, no differences were found regarding treatment selection or response according to sex; however, differences were observed in the rate of gastrointestinal adverse events, which was higher in women. Women have been reported to have a greater predisposition to functional GI disorders, such as irritable bowel syndrome and dyspepsia. Estradiol, the main female sex hormone, has been involved in increased visceral sensitivity and modulation of GI motility. In addition, higher testosterone levels have been associated with a lower risk of irritable bowel syndrome, which could partly explain the observed differences and should be considered when selecting treatments in which GI disorders are a frequent adverse effect.15,16
In conclusion, significant differences exist in the clinical signs and comorbidities of AD according to sex. Men presented greater disease severity measured by EASI and higher IgE levels, whereas women showed greater impairment in POEM scores, higher pruritus intensity, a higher frequency of anxiety and depression, and a higher rate of GI adverse events. These findings underscore the need to consider sex as a relevant factor in the progression and comprehensive management of AD.
Use of generative artificial intelligence in scientific writingNo artificial intelligence was used in the writing of this manuscript.
FundingThis study is promoted by the Fundación Piel Sana of the AEDV, which in turn receives financial support from pharmaceutical companies (such as Sanofi, AbbVie, Pfizer, and Almirall). Study planning and execution were conducted independently. The collaborating pharmaceutical companies were not involved whatsoever in the design, collection, management, analysis, or interpretation of data, nor in the preparation, review, or approval of the manuscript. The decision to submit the manuscript for publication was also made independently, without intervention from the collaborating pharmaceutical companies.
Conflicts of interestI. Castaño-González declared no conflicts of interest whatsoever.
A. Navarro-Bielsa has participated as advisor and/or investigator and/or speaker for: AbbVie, Almirall, Janssen, LEO Pharma, Sanofi, and Galderma.
Y. Gilaberte-Calzada has participated as advisor for Isdin, Roche Posay, and Galderma; as speaker for Almirall, Sanofi, Avène, Rilastil, Lilly, Uriage, Novartis, and Cantabria Labs; and has participated in research projects for Almirall, Sanofi, Pfizer, AbbVie, and LEO Pharma.
J.M. Carrascosa has participated as principal investigator/subinvestigator and/or received honoraria as speaker and/or member of expert committees or steering committees for AbbVie, Novartis, Janssen, Lilly, Sandoz, Amgen, Almirall, BMS, Boehringer Ingelheim, Biogen, and UCB.
M. Espasandín has participated in educational activities, courses, congress attendance, and lectures sponsored by AbbVie, Leo Pharma, Pfizer, Lilly, Almirall, and Sanofi.
A. González-Quesada has participated as consultant, speaker, and clinical trial investigator for AbbVie, Pfizer, Novartis, Sanofi, Boehringer, Bristol-Meyer, Leo-Pharma, and Janssen.
P. de la Cueva Dobao has acted as advisor and/or investigator and/or speaker for: AbbVie, Almirall, BMS, Boehringer, Celgene, Janssen, LEO Pharma, MSD, Novartis, Pfizer, Roche, Sanofi, and UCB.
P. Chicharro has participated in consultancies, advisory boards, and clinical trials organized by the following companies: Janssen Pharmaceuticals, Almirall, Sanofi Genzyme, Lilly, AbbVie, Novartis, Leo-Pharma, and Pfizer-Wyeth.
M. Elosua-González has participated as investigator and/or speaker for AbbVie, Lilly, Galderma, LEO Pharma, Pfizer, UCB Pharma, and Sanofi Genzyme.
L. Curto-Barredo has received honoraria for lectures and/or advisory activities from Sanofi, AbbVie, Leo Pharma, Almirall, Lilly, Novartis, and Uriach.
M. Munera-Campos has participated as investigator in clinical trials sponsored by Sanofi, AbbVie, Lilly, Leo-Pharma, Pfizer, Almirall, Galderma, and Novartis, and has received honoraria as speaker and consultant from Sanofi, Lilly, Leo Pharma, AbbVie, and Galderma.
A. Batalla has received honoraria and/or collaborated in educational activities, consultancy, or participation in clinical trials for AbbVie, Celgene, Faes Pharma, Isdin, Janssen, Leo Pharma, LETI Pharma, Lilly, Mylan, Novartis, Pfizer, Pierre Fabre, and Sanofi.
G. Roustan Gullón has received honoraria for lectures and/or advisory activities from Sanofi, AbbVie, Leo Pharma, Lilly, and Novartis.
C. Couselo-Rodríguez has participated as subinvestigator or speaker in projects sponsored by: AbbVie, Sanofi, Almirall, Leo-Pharma, Lilly, UCB, Novartis, Pierre Fabre, and Janssen.
M. Rodríguez Serna has participated in advisory activities for Sanofi, Pfizer, Leo, Novartis, and AbbVie.
M. Bertolín-Colilla has received honoraria for lectures and/or advisory activities from Sanofi and Leo Pharma.
A. Rosell-Díaz has received honoraria for lectures and/or advisory activities from Sanofi, AbbVie, and Leo Pharma.
A.M. Giménez-Arnau is or has recently been a speaker and/or advisor and/or has received research funding from Almirall, Amgen, AstraZeneca, Avène, Blue-Print, Celltrion, Celldex, Escient Pharmaceuticals, Genentech, GSK, Harmonic Bio, Incyte, Instituto Carlos III-FEDER, Jaspers, Leo Pharma, Menarini, Mitsubishi Tanabe Pharma, Noucor, Novartis, OVOIMMUNE, Pfizer, RAPT Therapeutics, Sanofi-Regeneron, Septerna, Servier, Thermo Fisher Scientific, and Uriach Pharma.
S. Martínez-Fernández has participated in educational activities and attended courses and congresses sponsored by Almirall, AbbVie, Janssen, Leo-Pharma, Lilly, Novartis, Sanofi, AstraZeneca, UCB, La Roche-Posay, and Pierre Fabre, and has participated as subinvestigator in clinical trials promoted by AbbVie, Pfizer, Sanofi, and Novartis.
J.F. Silvestre Salvador has collaborated as speaker, advisor, and/or investigator for: AbbVie, Almirall, Amgen, Astra Zeneca, Bristol Myers Squibb, Eli Lilly, Galderma, Incyte, Leo Pharma, Novartis, Pfizer, Regeneron, and Sanofi Genzyme.
We express our appreciation to all BIOBADATOP investigators for their commitment and for the rigorous collection of adverse events and other relevant clinical data.




